
Greening out is an acute adverse reaction to cannabis in which a person turns pale, sweaty, nauseated, and severely anxious after taking more THC than their tolerance handles. Most episodes resolve within a few hours.
The reaction combines two separate events. THC drops blood pressure while simultaneously overactivating threat circuitry, so fainting and panic arrive together.
Cannabis alone does not produce fatal overdose. The danger rises when cannabis is combined with alcohol or opioids, and that combination accounts for most greenouts that reach an emergency department.
How long does it last, and what actually helps someone through it?
Key Takeaways
- Fatal overdose from cannabis alone is not documented according to the Centers for Disease Control and Prevention. Greening out is frightening and physically miserable rather than lethal, and the danger rises sharply when cannabis is combined with alcohol or opioids.
- Most greening out episodes resolve within 30 minutes to 6 hours, though edibles extend the course toward 24 hours because oral THC absorbs slowly and unpredictably.
- Cannabis-related emergency department visits rose nearly 50% between 2019 and 2020 according to Truveta Research, and SAMHSA data show substance use disorder emergency visits climbing 42% among adults aged 18 to 34.
- The Cannabis Use Disorders Identification Test-Revised (CUDIT-R) scores hazardous use at 8 or above and possible cannabis use disorder at 12 or above across its 0 to 32 range.
- Florida emergency departments recorded marijuana exposure visits rising from 697 to 6,522 between 2016 and 2023, an 836% increase reported by the Florida Department of Health. That figure covers ages 0 to 17 rather than the adults Riverside Recovery treats, and it tracks rising product potency statewide.
What Is Greening Out?
Greening out describes an acute adverse reaction to cannabis in which a person becomes pale, nauseated, dizzy, and severely anxious after consuming more THC than their tolerance accommodates. The name comes from the greenish pallor that accompanies the drop in blood pressure.
Greening out is informal slang and appears nowhere in the DSM-5-TR. Clinicians classify the reaction as cannabis intoxication, and when anxiety dominates the presentation they classify it as cannabis-induced anxiety disorder. The underlying pattern of use may meet criteria for cannabis use disorder.
The reaction combines two separate physiological events. THC drops blood pressure while simultaneously activating threat-response circuitry, which produces fainting and panic at the same time.
Greening Out vs Whiteying
British and Australian cannabis users call the same reaction whiteying, naming the pallor rather than the greenish tint. Both terms describe identical physiology and carry no clinical distinction.
Some users reserve greening out for nausea-dominant episodes and whiteying for episodes dominated by fainting. That distinction reflects regional slang rather than any difference in mechanism or treatment.
What Causes Greening Out?
Greening out results from a THC dose exceeding what a person’s receptor system tolerates, and four separate factors determine whether it happens. Dose alone does not explain it.

The Biphasic THC Dose-Response Curve
THC follows a biphasic dose-response curve, reducing anxiety at low doses and generating anxiety at high doses through the same CB1 receptors. Cannabinoid pharmacologists including Ethan Russo describe this reversal as the defining feature of THC’s psychiatric profile.
Low-dose THC dampens amygdala reactivity, producing the calm users seek. Higher concentrations overactivate CB1 receptors in the amygdala and prefrontal cortex, which amplifies threat detection and produces the paranoia and panic that define a greenout.
How THC Drops Blood Pressure
THC dilates peripheral blood vessels and raises heart rate, a combination that produces orthostatic hypotension when a person stands. Reduced cerebral perfusion generates the lightheadedness, tunnel vision, and pallor that precede fainting.
Vasovagal syncope follows when the drop is steep enough, and the accompanying nausea and cold sweating come from the same autonomic response. Standing up quickly during peak intoxication is the single most common trigger for the fainting component.
Crossfading: Why Alcohol Multiplies the Risk
Combining cannabis with alcohol, which users call crossfading, produces a reaction more severe than either substance generates alone. Alcohol raises THC absorption into the bloodstream while independently causing vasodilation and vomiting.
Alcohol also suppresses the gag reflex, which converts cannabis-induced vomiting into an aspiration risk in anyone who loses consciousness. Crossfading accounts for a large share of the greenout episodes that reach emergency departments, and it is the scenario that turns a self-limiting reaction into a medical emergency.
Risk Factors That Raise the Odds
Factors that make greening out substantially more likely:
- Low or absent THC tolerance: People without recent regular exposure have higher CB1 receptor availability, so a given dose produces stronger effects.
- High-potency products: Concentrates, dabs, moon rocks, and semi-synthetic cannabinoids including THC-O acetate deliver doses per inhalation that flower does not approach.
- Edibles and delayed onset: Oral THC converts to the more potent metabolite 11-hydroxy-THC in the liver and takes 30 to 120 minutes to peak, which drives redosing before the first dose registers.
- Empty stomach and dehydration: Low blood volume worsens the orthostatic blood pressure drop that produces fainting.
- Pre-existing anxiety disorders: Baseline anxiety sensitivity amplifies the anxiogenic phase, which is why anxiety disorder treatment changes the risk picture.
How Long Does Greening Out Last?
Greening out duration depends primarily on route of administration, because inhaled and oral THC follow different absorption curves. The timeline below applies to adults.
- 0 to 15 minutes after inhalation: Symptoms escalate rapidly. Pallor, sweating, nausea, and rising heart rate appear, and anxiety builds as the person recognizes something is wrong.
- 15 to 45 minutes: Symptoms peak. Fainting risk concentrates here, along with vomiting, depersonalization, and the sensation users describe as the spins.
- 45 minutes to 3 hours: Acute symptoms subside gradually. Nausea and dizziness resolve before the anxiety does, and most people can sit up without lightheadedness by the end of this window.
- 3 to 6 hours: Residual effects persist. Fatigue, mild nausea, and emotional rawness continue while acute distress has passed.
- 6 to 24 hours, edibles and heavy doses: Oral THC extends the entire course. Grogginess, cognitive fog, and low mood can last a full day, an aftermath users call a weed hangover.

Greening Out Symptoms by Severity
Greening out produces symptoms across autonomic, gastrointestinal, and psychiatric systems simultaneously. Symptoms sort into three tiers.
Common Symptoms
Symptoms present in most greening out episodes:
- Pallor and cold sweating: Peripheral vasodilation and autonomic activation drain color from the face and produce clammy skin.
- Nausea and vomiting: THC action on the area postrema in the brainstem triggers emesis at high doses, reversing its antiemetic effect at therapeutic doses.
- Dizziness and the spins: Orthostatic hypotension reduces cerebral perfusion, producing the rotational sensation users report when lying down.
- Tachycardia: THC elevates heart rate by 20 to 50 beats per minute, which many people interpret as a cardiac event.
- Anxiety and paranoia: High-dose CB1 activation in the amygdala amplifies threat perception, generating acute fear disproportionate to the situation.
Severe Symptoms and Emergency Warning Signs
A minority of episodes cross from miserable into medically dangerous, almost always when cannabis is combined with another substance. Recognizing the threshold prevents harm.
Call 911 immediately for any of the following:
- Chest pain or pressure. Cannabis-induced tachycardia can precipitate cardiac events in people with underlying coronary disease.
- Loss of consciousness that does not resolve within seconds. Brief fainting on standing differs from sustained unresponsiveness.
- Vomiting while unconscious or unable to stay awake. Aspiration risk rises sharply, particularly with alcohol involved.
- Seizure activity. Seizures indicate a cause other than cannabis alone and require immediate evaluation.
- Active psychosis. Hallucinations, or a fixed belief that others intend harm, warrant emergency psychiatric assessment.
- Suspected combination with opioids or alcohol poisoning. Slow or irregular breathing, blue lips, or unrousable sleep indicate respiratory depression rather than a greenout.
After Effects
Effects that persist after the acute episode resolves:
- Cognitive fog and fatigue: Residual THC and its metabolites impair concentration and drive exhaustion for up to 24 hours.
- Lingering anxiety: A severe greenout sensitizes threat-response circuitry, and some people develop anticipatory anxiety about cannabis afterward.
- Aversion or continued use: Some people stop using cannabis entirely after one episode, while others resume within days, and the second pattern signals possible cannabis use disorder.
- Muscle soreness and dehydration: Repeated vomiting depletes fluid and electrolytes and leaves abdominal muscles sore.
Greening Out vs a Panic Attack
Greening out and panic attacks share most psychiatric symptoms, and people experiencing either frequently believe they are dying. The autonomic signs and the cannabis timeline separate them.
| Feature | Greening out | Panic attack |
|---|---|---|
| Trigger | Cannabis consumption within the previous 2 hours | Often no identifiable trigger |
| Skin | Pale, cold, clammy, greenish cast | Flushed or normal |
| Blood pressure | Drops, producing fainting on standing | Rises or stays stable |
| Nausea and vomiting | Common and often prominent | Possible but usually mild |
| Peak duration | 15 to 45 minutes, resolving over hours | Peaks within 10 minutes, resolves in 20 to 30 |
| Response to reassurance | Helps but does not shorten physical course | Frequently shortens the episode |
The blood pressure direction is the most reliable distinguishing sign. Panic attacks raise blood pressure, while greening out lowers it, which is why fainting characterizes one and not the other.
What to Do When Someone Greens Out
Greening out has no antidote, and no medication reverses acute THC. Supportive care and time resolve it.
- Move them somewhere calm and dim. Reducing sensory input lowers the stimulation that feeds paranoia and panic.
- Lay them down with legs slightly elevated. This position restores cerebral perfusion and stops the lightheadedness that leads to fainting.
- Give small sips of water or a sports drink. Hydration counteracts the blood pressure drop, and small volumes reduce the chance of vomiting.
- Stay with them and state plainly that this will pass. Verbal reassurance addresses the fear of dying that dominates the experience.
- Position them on their side if they vomit or become drowsy. The recovery position protects the airway against aspiration.
- Stop all further consumption, including alcohol. Adding any substance extends and deepens the episode.
- Call 911 if any emergency sign above appears. Chest pain, sustained unconsciousness, seizure, or psychosis require professional care rather than time.
Two widely repeated remedies lack evidence. Cold showers risk fainting from an already low blood pressure, and chewing black peppercorns for beta-caryophyllene rests on a theoretical CB2 mechanism that no controlled trial supports.
No antidote reverses acute THC intoxication, a point National Institute on Drug Abuse research confirms. Supportive care and elapsed time remain the only effective response.
Treatment for Cannabis Use Disorder
A single greenout does not indicate a substance use disorder, while repeated episodes signal a pattern worth assessing. Treatment addresses the underlying use rather than the acute reaction.
How Cannabis Use Disorder Is Diagnosed
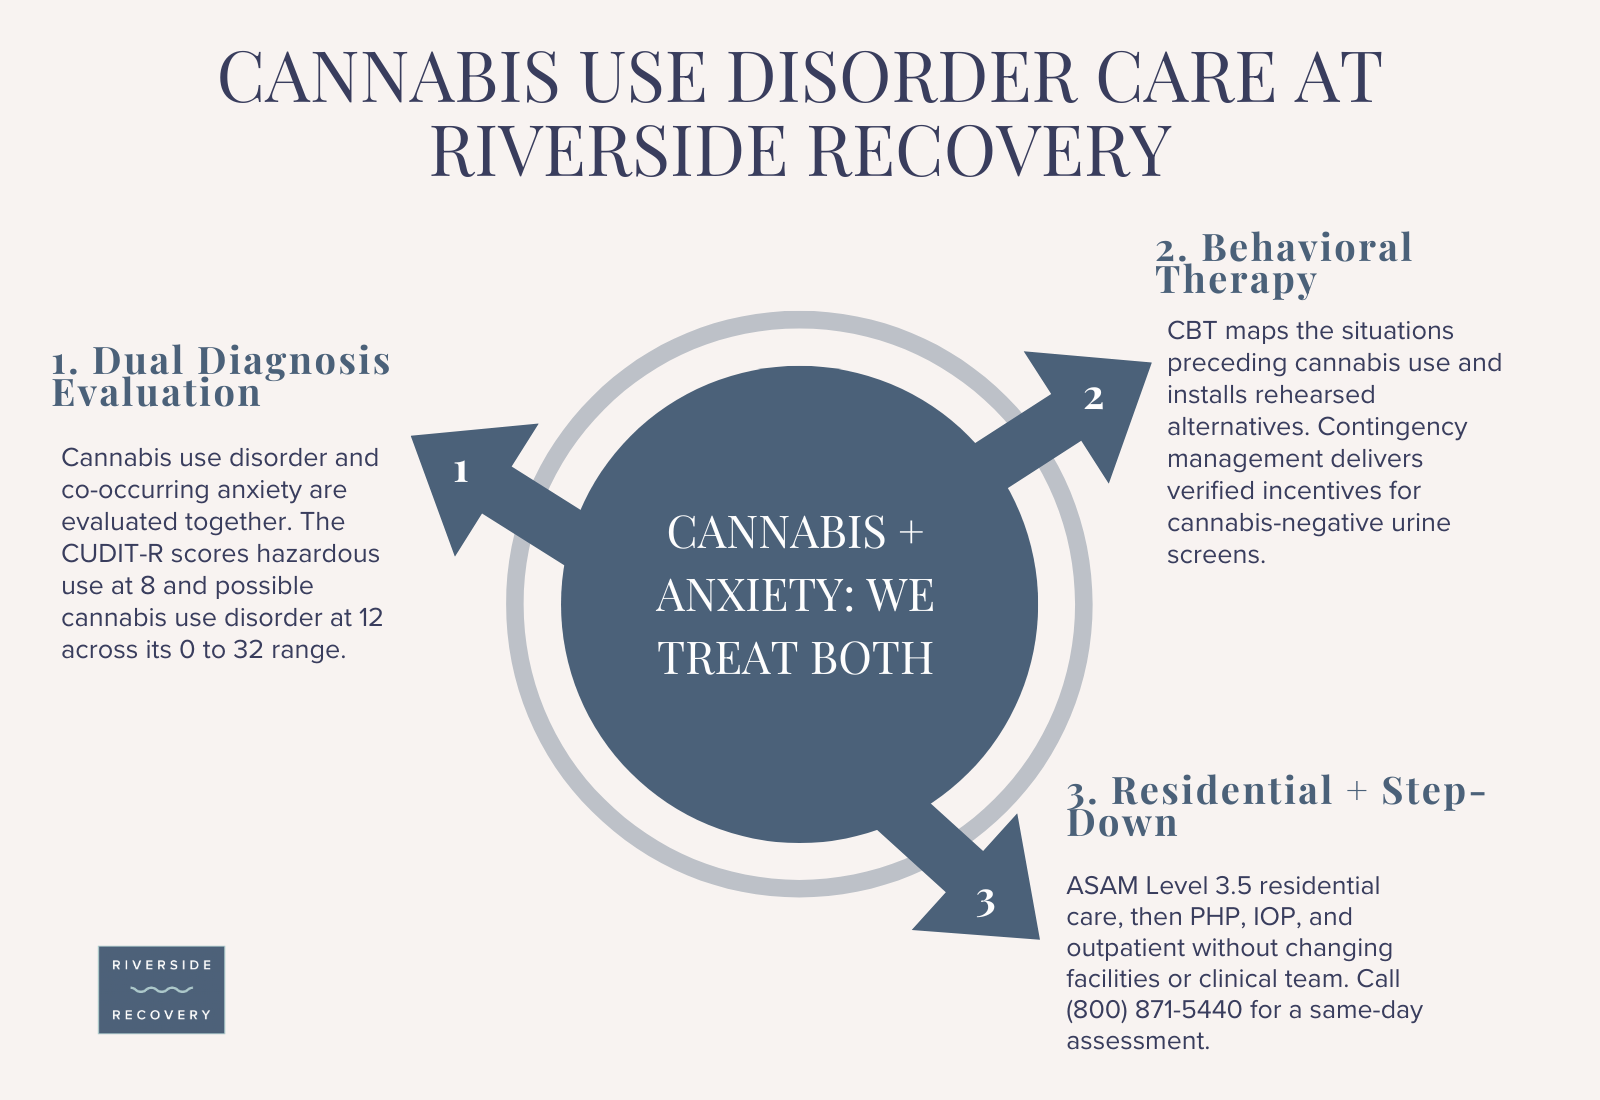
The Cannabis Use Disorders Identification Test-Revised (CUDIT-R), developed by Adamson and colleagues in 2010, measures cannabis-related harm across 8 self-report items covering the past 6 months. Scores run 0 to 32, with 8 or above indicating hazardous use and 12 or above indicating possible cannabis use disorder.
DSM-5-TR grades cannabis use disorder as mild, moderate, or severe according to how many of 11 criteria a person meets. Repeated greenouts frequently satisfy the criterion covering continued use despite recurrent physical or psychological harm.
First-Line Behavioral Therapies
Therapies with the strongest evidence for cannabis use disorder:
- Cognitive behavioral therapy (CBT): CBT maps the situations and beliefs preceding cannabis use and substitutes rehearsed alternative responses.
- Contingency management: Verified incentives for cannabis-negative urine screens generate the largest effect sizes of any cannabis use disorder intervention.
- Motivational enhancement therapy: Motivational interviewing converts ambivalence after a frightening episode into engagement with treatment.
Medication and Symptom Management
No medication holds FDA approval for cannabis use disorder, which distinguishes it from opioid and alcohol use disorder. Prescribers address withdrawal symptoms rather than the disorder itself.
Cannabis withdrawal produces irritability, insomnia, appetite loss, and vivid dreams for 1 to 2 weeks after cessation, managed symptomatically. Benzodiazepines including lorazepam calm severe agitation in emergency settings, prescribed short-term and off-label.
Emerging and Investigational Treatments
Treatments under active investigation:
- Cannabidiol (CBD) as a THC counteractant: Controlled trials are testing pharmaceutical-grade CBD for cannabis use disorder, with mixed results and no FDA approval for this indication.
- N-acetylcysteine (NAC): NAC restores glutamate regulation in the nucleus accumbens and benefited adolescents in trials, though adult results reported by Gray and colleagues in 2017 did not replicate. Use remains off-label.
- Gabapentin: Small trials examined gabapentin for cannabis withdrawal and craving, and its use remains investigational.
Treatment at Riverside Recovery of Tampa
Riverside Recovery of Tampa treats adults 18 and older for substance use disorders and co-occurring mental health conditions across a full continuum of care. The 60,000-square-foot facility sits on the Hillsborough River near downtown Tampa and has operated since 2017.
The Joint Commission accredits Riverside Recovery, and CARF International accredits the facility at American Society of Addiction Medicine (ASAM) Level 3.5 for residential treatment. Riverside Recovery also carries LegitScript certification and belongs to the National Association of Addiction Treatment Providers.
The clinical model is abstinence-based and rooted in 12-step principles. Patients choose among Alcoholics Anonymous, Narcotics Anonymous, SMART Recovery, Dharma Recovery, and Celebrate Recovery.
“A greenout brings people in more often than the cannabis use itself does, because the episode is what finally frightens them,” says Jackie Dowgiallo, LMHC, CAP, Clinical Director at Riverside Recovery of Tampa. “The clinical question is always whether it happened once at an unfamiliar dose or whether it keeps happening, because those two patterns need different care.”
Medical Detoxification
Riverside Recovery provides 24-hour medically supervised medical detox overseen by Medical Director Dr. Michael Sore, MD, with the nursing team present throughout. Adults who green out after crossfading frequently need alcohol withdrawal assessment as well, which uses different protocols and carries genuine seizure risk.
Residential Treatment
Residential treatment at ASAM Level 3.5 delivers structured daily programming beginning with guided meditation and exercise, followed by therapeutic groups, a 12-step meeting, and a daily goal review. Modalities include CBT, DBT, motivational interviewing, mindfulness-based relapse prevention, experiential therapy, trauma resolution therapy, and Accelerated Resolution Therapy (ART).
Dual Diagnosis Care
Riverside Recovery treats co-occurring mental health conditions alongside substance use disorders rather than sequentially. Determining whether an anxiety disorder preceded cannabis use or developed from it changes which condition treatment targets first.
Outpatient Programming
Day/night partial hospitalization, intensive outpatient, and standard outpatient therapy extend clinical contact after residential discharge. Patients move between levels of care without changing facilities or losing their clinical team.
Frequently Asked Questions
How long does greening out last?
Inhaled cannabis produces episodes lasting 30 minutes to 6 hours, with peak symptoms between 15 and 45 minutes. Edibles extend the course toward 24 hours because oral THC absorbs slowly and converts to a more potent liver metabolite.
Can you die from greening out?
Fatal overdose from cannabis alone is not documented according to the CDC. Deaths connected to greenout episodes involve other factors, most commonly aspiration of vomit while unconscious, alcohol poisoning, or an unrelated cardiac event.
What does greening out feel like?
People describe the room spinning, drenching cold sweats, overwhelming nausea, a racing heart, and certainty that they are dying. Detachment from body and surroundings is common, which clinicians term depersonalization and derealization.
Can you green out from edibles?
Yes, and edibles cause some of the most severe episodes. Oral THC takes 30 to 120 minutes to peak, so people frequently take a second dose before the first registers, and the liver converts it to a more potent metabolite.
Does eating or showering help?
Food does not shorten an episode, though small sips of water or an electrolyte drink counteract the blood pressure drop. Cold showers risk fainting from already low blood pressure, so lying down with legs elevated is safer.
Do first-time cannabis users green out more often?
Yes. People without established tolerance have higher CB1 receptor availability, so a standard dose produces stronger effects. Regular users green out primarily after switching to concentrates or edibles at a familiar-seeming amount.
What is crossfading and why is it dangerous?
Crossfading means combining cannabis with alcohol. Alcohol increases THC absorption, independently lowers blood pressure, and suppresses the gag reflex, which converts cannabis-induced vomiting into an aspiration risk.
Is greening out a sign of addiction?
One episode at an unfamiliar dose is not. Repeated greenouts indicate continued use despite recurrent harm, which is a DSM-5-TR criterion for cannabis use disorder and warrants CUDIT-R screening.
References
- Adamson, S. J., Kay-Lambkin, F. J., Baker, A. L., Lewin, T. J., Thornton, L., Kelly, B. J., & Sellman, J. D. (2010). An improved brief measure of cannabis misuse: The Cannabis Use Disorders Identification Test-Revised (CUDIT-R). Drug and Alcohol Dependence, 110(1-2), 137-143.
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Publishing.
- Centers for Disease Control and Prevention. (2024). Cannabis and public health: Health effects. U.S. Department of Health and Human Services.
- ElSohly, M. A., Mehmedic, Z., Foster, S., Gon, C., Chandra, S., & Church, J. C. (2016). Changes in cannabis potency over the last 2 decades (1995-2014): Analysis of current data in the United States. Biological Psychiatry, 79(7), 613-619.
- Florida Department of Health. (2024, October 22). Guidance for non-medical marijuana use in adolescents. State Surgeon General.
- Gray, K. M., Sonne, S. C., McClure, E. A., Ghitza, U. E., Matthews, A. G., McRae-Clark, A. L., & Levin, F. R. (2017). A randomized placebo-controlled trial of N-acetylcysteine for cannabis use disorder in adults. Drug and Alcohol Dependence, 177, 249-257.
- National Institute on Drug Abuse. (2024). Cannabis (marijuana) research report. National Institutes of Health.
- Substance Abuse and Mental Health Services Administration. (2024). Key substance use and mental health indicators in the United States: Results from the 2023 National Survey on Drug Use and Health (HHS Publication No. PEP24-07-021).
- Truveta Research. (2024). Cannabis-involved emergency department visits following legalization. Truveta.