
Precipitated withdrawal is the sudden onset of severe opioid withdrawal caused by taking buprenorphine, naloxone, or naltrexone while a stronger opioid still occupies the receptors. It begins within one to two hours rather than building over days.
Timing rather than dose decides whether it happens. The same buprenorphine dose that triggers severe withdrawal at hour four produces relief at hour eighteen.
It is also preventable and short-lived. Clinicians time induction using a withdrawal score rather than a fixed number of hours, and the episode typically resolves inside a day.
What causes the reaction, and how long should someone actually wait?
Key Takeaways
- Precipitated withdrawal is preventable and short-lived. It begins within 1 to 2 hours of the triggering dose and typically resolves within 6 to 24 hours with medical management.
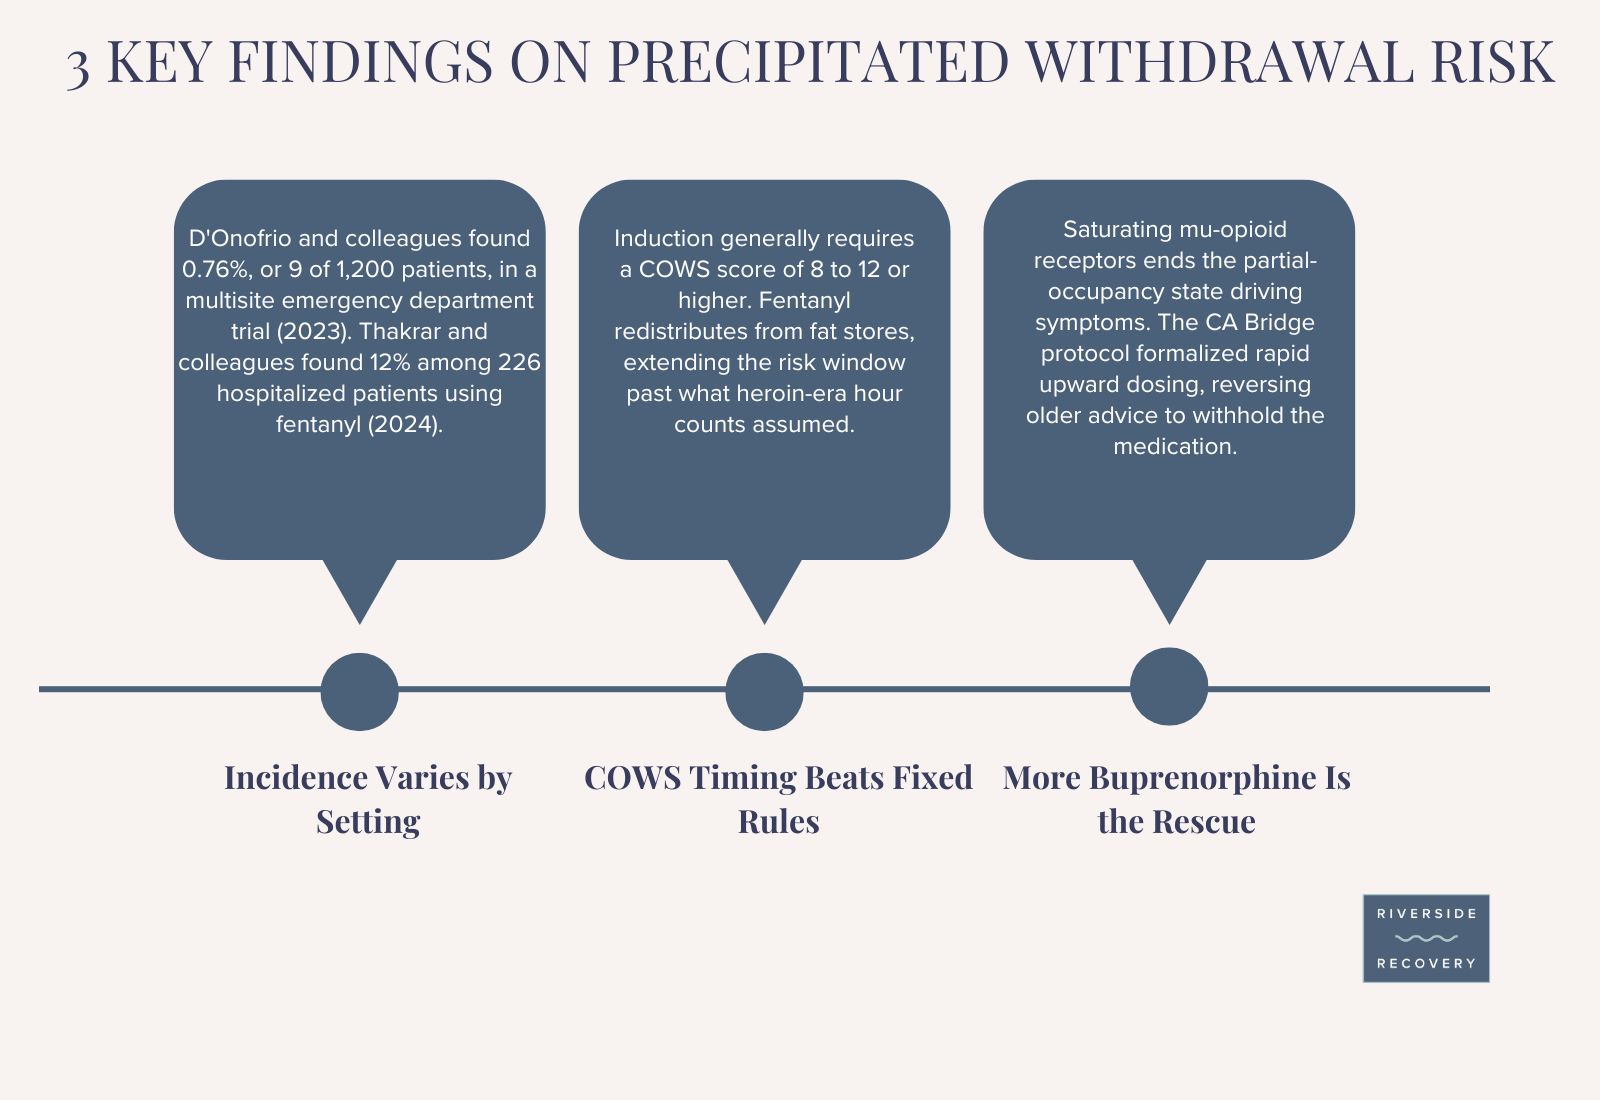
- Reported incidence varies widely by clinical setting. D’Onofrio and colleagues documented 0.76%, or 9 of 1,200 patients, in a multisite emergency department trial published in 2023. Thakrar and colleagues found 12% of 226 hospitalized patients using fentanyl in JAMA Network Open in 2024.
- The Clinical Opiate Withdrawal Scale (COWS) scores 11 items from 0 to 48, and buprenorphine induction generally requires a score of 8 to 12 or higher before the first dose to reduce risk.
- Counterintuitively, additional buprenorphine now serves as the standard rescue treatment once precipitated withdrawal is established, rather than stopping the medication.
- No verified Florida statistic exists for buprenorphine-precipitated withdrawal specifically. The CDC recorded 5,180 Florida opioid overdose deaths as of December 2023, and the Florida Medical Examiners Commission reported opioid-related deaths falling 26% in 2024 compared with 2023.
What Is Precipitated Withdrawal?
Precipitated withdrawal is the abrupt onset of severe opioid withdrawal caused by taking buprenorphine, naloxone, or naltrexone while a full opioid agonist still occupies the mu-opioid receptors. The medication forces the stronger opioid off the receptor and replaces it with weaker or no activation.
Precipitated withdrawal is a pharmacological event rather than a DSM-5-TR diagnosis. DSM-5-TR classifies opioid withdrawal as a diagnosis and classifies the underlying condition as opioid use disorder, the correct clinical terminology.
Timing rather than dose determines whether it happens. The same buprenorphine dose that triggers severe withdrawal at hour 4 produces relief at hour 18.
How Buprenorphine Displaces Full Agonists
Buprenorphine binds mu-opioid receptors with higher affinity than heroin, fentanyl, oxycodone, or hydrocodone, meaning it wins the competition for receptor occupancy. Buprenorphine simultaneously produces lower intrinsic activity than those drugs, a property clinicians call the ceiling effect.
That combination creates the problem. Buprenorphine evicts a strongly activating drug and substitutes weak activation, and the receptor system registers the sudden drop as immediate, severe withdrawal rather than as gradual tapering.
What Causes Precipitated Withdrawal?
Receptor pharmacology, the specific opioid involved, and the medication administered together determine risk. Three causal layers apply.
Binding Affinity and Intrinsic Activity
Mu-opioid receptors respond to two independent drug properties. Binding affinity determines which molecule occupies the receptor, while intrinsic activity determines how strongly that molecule activates it once bound.
Full agonists including fentanyl, heroin, oxycodone, and morphine produce maximal receptor activation. Buprenorphine, a partial agonist, produces submaximal activation regardless of dose, and naloxone and naltrexone produce none at all as pure antagonists.
Why Fentanyl Changed the Timing
Fentanyl is highly lipophilic, meaning it accumulates in body fat and redistributes into the bloodstream for days after last use. That storage extends the window during which buprenorphine can trigger precipitated withdrawal well beyond what heroin-era protocols assumed.
Rigid waiting rules fail in this context. A person using fentanyl may still carry meaningful receptor occupancy at 24 or 36 hours, which is why clinical assessment replaced fixed hour counts as the standard for timing induction.
Naloxone and Naltrexone as Triggers
The three medication classes that precipitate withdrawal:
- Buprenorphine products: Suboxone, Subutex, and Sublocade all contain buprenorphine and displace full agonists through high receptor affinity.
- Naltrexone: Vivitrol, the monthly extended-release naltrexone injection, blocks receptors completely and produces the most severe precipitated withdrawal of any agent, which is why it requires full detoxification first.
- Naloxone: Emergency naloxone reverses overdose by evicting opioids from receptors, and the resulting withdrawal is expected and clinically acceptable because it restores breathing.
The naloxone contained within Suboxone serves a different purpose than emergency naloxone. It functions as an abuse deterrent that activates only if the tablet or film is injected, and it does not drive precipitated withdrawal when taken as prescribed.
Precipitated Withdrawal Timeline
Precipitated withdrawal follows a compressed and predictable course, unlike spontaneous withdrawal which builds over days. The timeline below applies after a triggering buprenorphine dose.
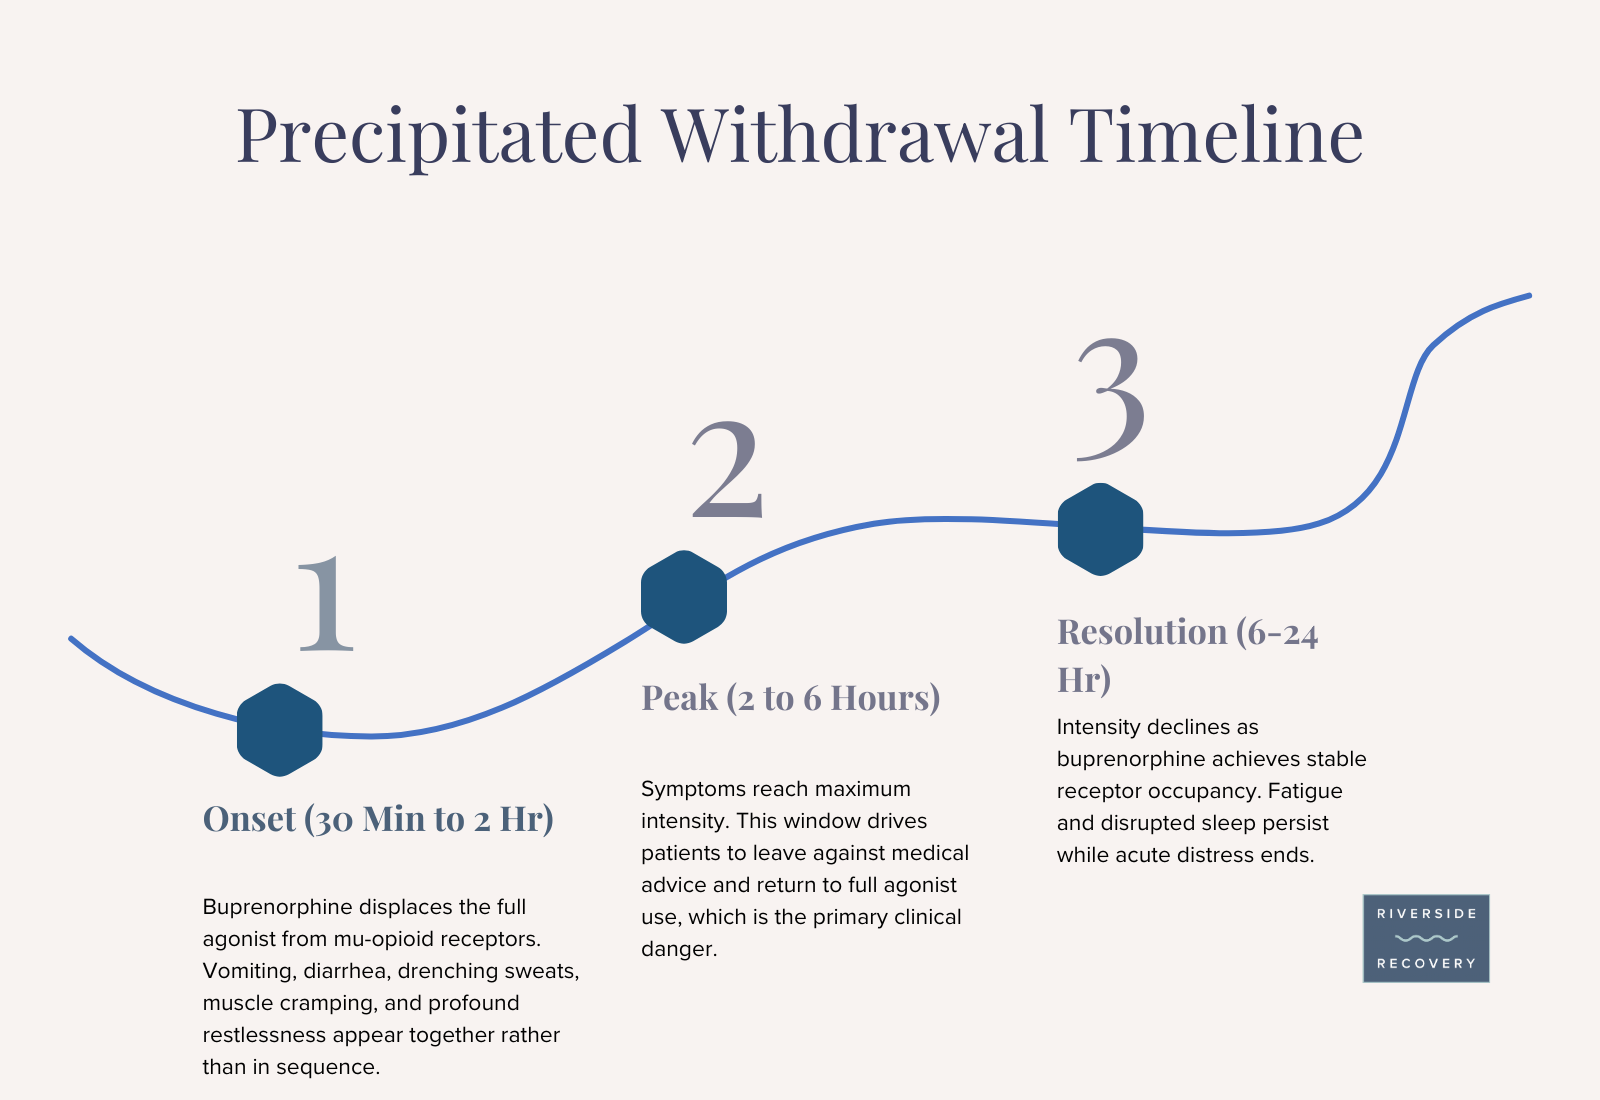
- 0 to 30 minutes: Buprenorphine reaches the mu-opioid receptors and begins displacing the full agonist. Most people feel nothing unusual yet.
- 30 minutes to 2 hours: Symptoms begin abruptly and escalate fast. Vomiting, diarrhea, sweating, muscle cramping, and profound restlessness appear together rather than in sequence.
- 2 to 6 hours: Symptoms reach peak intensity. This window drives patients to leave against medical advice and to return to full agonist use, which is the primary clinical danger.
- 6 to 12 hours: Intensity begins declining as buprenorphine achieves stable receptor occupancy. Additional buprenorphine given during this period shortens the course rather than extending it.
- 12 to 24 hours: Most symptoms resolve. Fatigue, mild nausea, and disrupted sleep persist while acute distress has ended.
- 24 to 72 hours: Residual symptoms clear and buprenorphine maintenance proceeds normally at an established dose.
Precipitated vs Spontaneous Withdrawal
Both conditions produce the same symptoms through entirely different mechanisms, and distinguishing them determines treatment. Onset speed is the clearest signal.
| Feature | Precipitated withdrawal | Spontaneous withdrawal |
|---|---|---|
| Cause | Medication displaces opioid from receptors | Opioid clears the body naturally |
| Onset | 1 to 2 hours after the triggering dose | 6 to 30 hours after last use, varies by drug |
| Escalation | Abrupt, symptoms peak within hours | Gradual, symptoms build over 1 to 3 days |
| Peak severity | Often more intense than spontaneous | Severe but builds predictably |
| Duration | 6 to 24 hours | 5 to 10 days for short-acting opioids |
| Treatment | Additional buprenorphine, supportive medication | Buprenorphine induction, comfort medication |
Spontaneous withdrawal is the state clinicians deliberately wait for before starting buprenorphine. A COWS score reflecting genuine spontaneous withdrawal signals that receptors have cleared enough for safe induction.
Precipitated Withdrawal Symptoms by Severity
Precipitated withdrawal produces gastrointestinal, autonomic, and neurological symptoms simultaneously and at greater intensity than most patients have previously experienced. Symptoms sort into three tiers.
Common Symptoms
Symptoms present in nearly all precipitated withdrawal episodes:
- Vomiting and diarrhea: Loss of receptor activation in the enteric nervous system produces simultaneous upper and lower gastrointestinal expulsion.
- Severe muscle and joint pain: Withdrawal removes opioid suppression of pain signaling, and patients describe deep aching in the legs and back.
- Profuse sweating and gooseflesh: Autonomic surge produces drenching sweats alternating with chills and piloerection.
- Extreme restlessness: Akathisia-like agitation makes sitting still impossible, and clinicians treat it as a core COWS item.
- Anxiety and irritability: Noradrenergic overactivity in the locus coeruleus generates acute anxiety and emotional volatility.
Severe Symptoms and Emergency Signs
Opioid withdrawal rarely threatens life in otherwise healthy adults, which distinguishes it from alcohol and benzodiazepine withdrawal. Complications arise from fluid loss and from what patients do to escape the symptoms.
Seek immediate medical attention for any of the following:
- Vomiting and diarrhea that prevent any fluid intake for 8 hours or longer. Volume depletion produces electrolyte derangement and acute kidney injury.
- Confusion or altered consciousness. These signs indicate electrolyte disturbance or another cause rather than withdrawal alone.
- Chest pain or irregular heartbeat. Autonomic surge and electrolyte loss together can destabilize cardiac rhythm.
- Seizure activity. Seizures are not a feature of opioid withdrawal and signal benzodiazepine or alcohol withdrawal occurring at the same time.
- Return to full agonist use during the episode. Using fentanyl or heroin to stop precipitated withdrawal carries acute overdose risk, because buprenorphine already occupies receptors and dosing escalates to overcome it.
That final risk is the reason precipitated withdrawal matters clinically. The event itself is survivable, while the relapse it drives is the mechanism through which it causes death.
Long-Term Consequences
Consequences that follow an episode of precipitated withdrawal:
- Treatment dropout: Patients who experience precipitated withdrawal frequently refuse buprenorphine permanently, closing off the most effective medication for opioid use disorder.
- Elevated overdose risk: Returning to full agonists after any abstinence lowers tolerance, and prior doses become lethal.
- Loss of trust in medical care: A patient who felt worse after taking prescribed medication frequently disengages from clinical settings entirely.
- Delayed recovery entry: Each failed induction attempt postpones stable medication-assisted treatment by weeks or months.
How the COWS Score Prevents Precipitated Withdrawal
Clinicians time buprenorphine induction using a validated withdrawal scale rather than a fixed number of hours since last use. The COWS is the standard instrument.
The Clinical Opiate Withdrawal Scale (COWS), developed by Donald Wesson and Walter Ling in 2003, scores 11 clinician-observed items. Total scores run 0 to 48.
The 11 scored items are resting pulse, sweating, restlessness, pupil size, bone or joint aches, runny nose, gastrointestinal upset, tremor, yawning, anxiety, and gooseflesh. A clinician records each item rather than relying on patient self-report.
COWS score interpretation:
- 5 to 12, mild withdrawal: Early objective signs are present, and some clinicians consider induction at the upper end of this range.
- 13 to 24, moderate withdrawal: This range provides a comfortable margin for standard buprenorphine induction.
- 25 to 36, moderately severe withdrawal: Induction is clearly appropriate and symptom relief is typically rapid.
- Above 36, severe withdrawal: Withdrawal is advanced, and buprenorphine produces substantial relief.
Buprenorphine induction generally requires a COWS score of 8 to 12 or higher, with many clinicians preferring 10 to 13 in the fentanyl era. The Subjective Opiate Withdrawal Scale (SOWS) provides a companion patient-reported measure alongside clinician COWS scoring.
Treatment and Prevention of Precipitated Withdrawal
Prevention through correct timing is the primary strategy, and established episodes respond to treatment. Four tiers apply.
First-Line: COWS-Guided Standard Induction
The components of a standard buprenorphine induction:
- Clinical assessment before the first dose: A clinician confirms objective withdrawal signs and records a COWS score rather than relying on the patient’s report of last use.
- Substance-specific timing: Short-acting opioids require roughly 12 to 24 hours of abstinence, while fentanyl frequently requires longer because it redistributes from fat stores.
- Incremental dosing: Prescribers give a small initial dose, reassess after 1 to 2 hours, and titrate upward based on response.
- Behavioral therapy from the start: Medication combined with counseling produces better retention than medication alone.
Pharmacological Management of Established Precipitated Withdrawal
Treatment reverses the intuitive response. Giving more buprenorphine, rather than withholding it, is now standard practice because full receptor saturation ends the partial-occupancy state driving symptoms.
Medications used to manage an active episode:
- Additional buprenorphine: Rapid upward dosing saturates mu-opioid receptors and shortens the episode, an approach the CA Bridge protocol formalized for emergency settings.
- Clonidine: This alpha-2 agonist suppresses the noradrenergic surge driving sweating, anxiety, and elevated heart rate.
- Ondansetron and antiemetics: These control vomiting and protect against the dehydration that produces complications.
- Loperamide and antidiarrheals: These reduce fluid loss from the lower gastrointestinal tract.
- Intravenous fluids: Volume replacement corrects the dehydration and electrolyte loss that severe episodes produce.
Second-Line: Low-Dose Bernese Induction
Robert Hämmig and colleagues in Bern, Switzerland published the low-dose overlapping induction method in Substance Abuse and Rehabilitation in 2016. The Bernese method starts buprenorphine at roughly 0.2 to 0.5 mg while the patient continues their full agonist, then titrates upward over days.
Because each buprenorphine increment is small, receptor displacement happens gradually and produces no withdrawal spike. Clinicians also call this approach microdosing or microinduction, and it removes the requirement to be in withdrawal before starting.
Emerging and Investigational Approaches
Approaches under active clinical investigation:
- High-dose induction: Starting at 8 to 16 mg or above produced low precipitated withdrawal rates in emergency department studies and is increasingly used for fentanyl-exposed patients.
- Extended-release buprenorphine pathways: Protocols initiating Sublocade earlier in treatment are under study, currently requiring sublingual buprenorphine tolerance first.
- Ketamine-assisted induction: Case series describe ketamine easing the transition through induction, an investigational approach without controlled trial support.
- Pooled incidence research: Gregory and colleagues published a systematic review in Addiction in 2025 quantifying precipitated withdrawal rates across settings, which is refining protocol guidance.
Guidance from the Substance Abuse and Mental Health Services Administration emphasizes clinical judgment over fixed waiting periods, a position National Institute on Drug Abuse research supports. Buprenorphine induction should never be combined with benzodiazepines or alcohol because the combination depresses respiration.
Treatment at Riverside Recovery of Tampa
Riverside Recovery of Tampa treats adults 18 and older for substance use disorders and co-occurring mental health conditions across a full continuum of care. The 60,000-square-foot facility sits on the Hillsborough River near downtown Tampa and has operated since 2017.
The Joint Commission accredits Riverside Recovery, and CARF International accredits the facility at American Society of Addiction Medicine (ASAM) Level 3.5 for residential treatment. Riverside Recovery also carries LegitScript certification and belongs to the National Association of Addiction Treatment Providers.
Medication decisions occur under the supervision of Medical Director Dr. Michael Sore, MD. The medical team conducts a comprehensive evaluation before selecting any medication.
“The people most afraid of starting buprenorphine are usually the ones who tried it too early on their own and got very sick,” says Dr. Michael Sore, MD, Medical Director at Riverside Recovery of Tampa. “Induction timed by clinical assessment rather than by a number of hours is what separates a difficult day from a failed attempt at treatment.”
Medical Detoxification
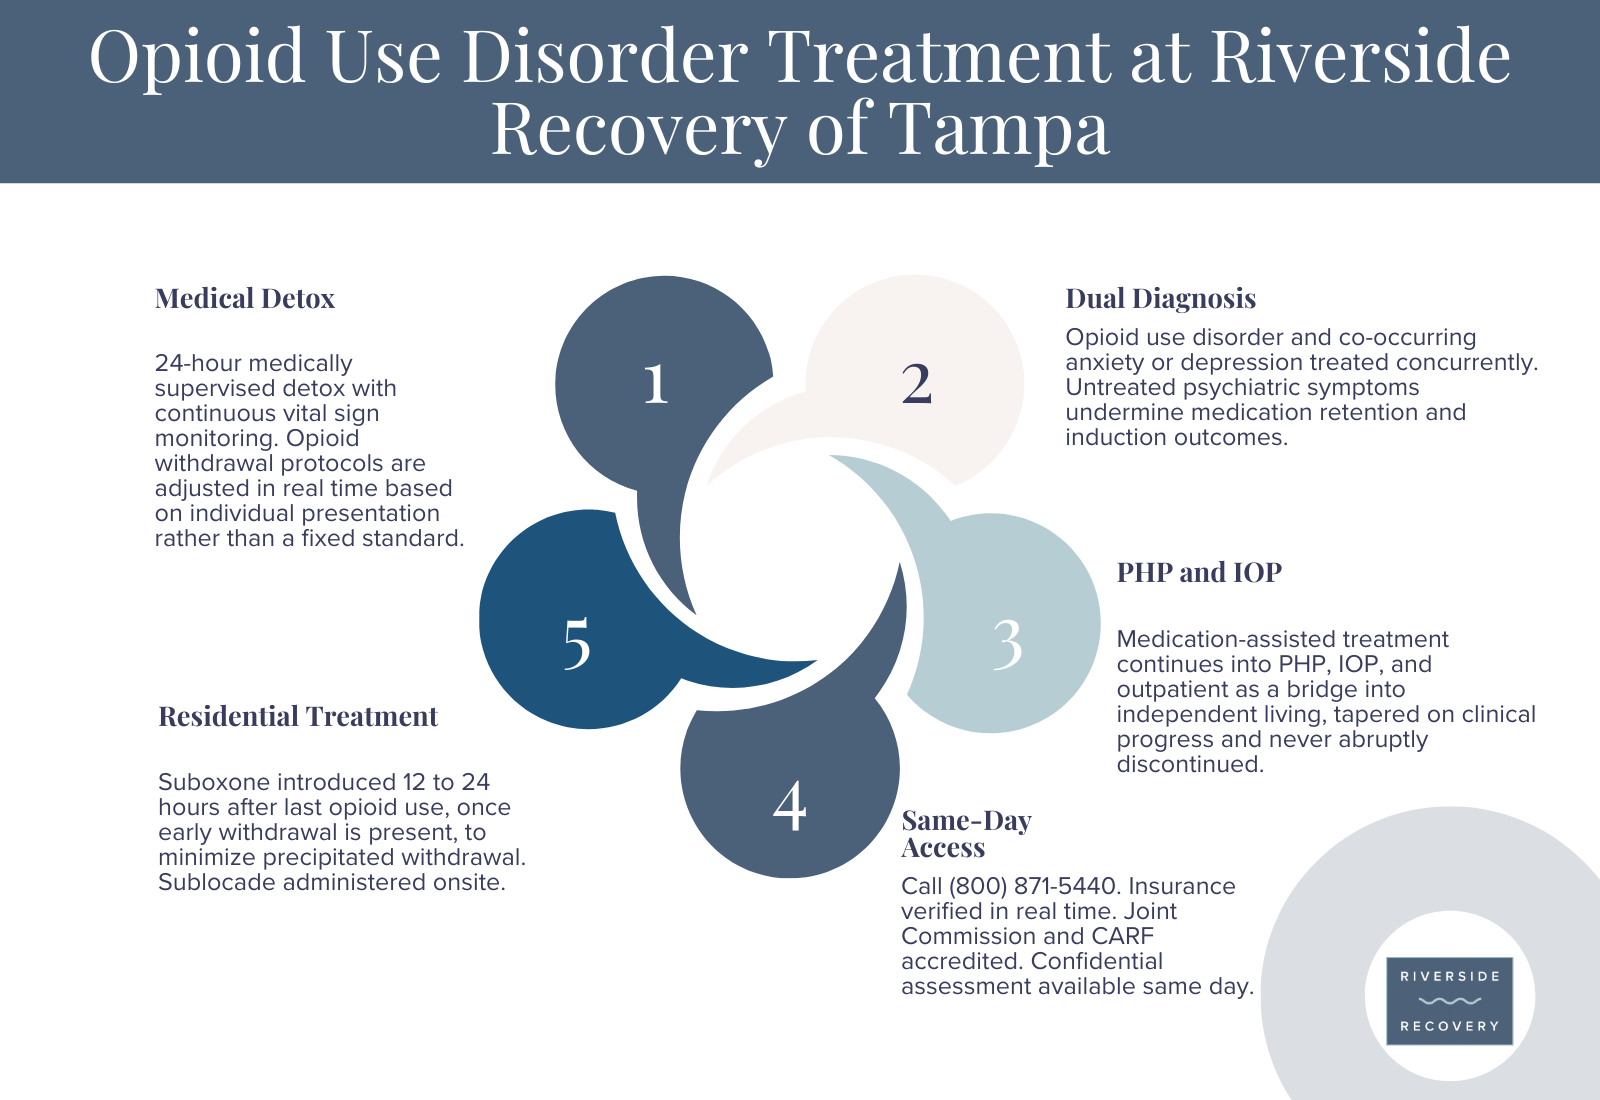
Riverside Recovery provides 24-hour medically supervised medical detox with continuous vital sign monitoring and nursing presence throughout. Opioid withdrawal protocols are adjusted in real time based on individual presentation rather than applied as a fixed standard.
Medication-Assisted Treatment
Riverside Recovery administers Suboxone under medical supervision, typically introduced 12 to 24 hours after last opioid use once early withdrawal symptoms are present, specifically to minimize precipitated withdrawal. Dosage is adjusted by clinical response and tapered gradually rather than discontinued abruptly.
Medication options available onsite:
- Suboxone (buprenorphine and naloxone): The primary medication for opioid use disorder at Riverside Recovery, delivering the full induction-to-taper protocol in one facility.
- Sublocade (extended-release buprenorphine): A once-monthly injection administered onsite by the medical team, well suited to patients moving from residential into outpatient care.
- Vivitrol (extended-release naltrexone): Initiated only after full detoxification, typically 7 or more days after last opioid use, to avoid precipitating severe withdrawal.
- Methadone in the detox context: Riverside Recovery manages methadone during detox but does not administer methadone maintenance as an ongoing protocol. Patients arriving on methadone maintenance typically require a pre-admission taper, and dose restrictions apply.
Residential Treatment
Residential treatment at ASAM Level 3.5 pairs medication with CBT, DBT, motivational interviewing, mindfulness-based relapse prevention, trauma resolution therapy, and Accelerated Resolution Therapy (ART). Medication-assisted treatment continues into intensive outpatient programming as a bridge into independent living.
Dual Diagnosis Care
Riverside Recovery treats co-occurring mental health conditions concurrently with opioid use disorder. Untreated anxiety and depression undermine medication retention, which makes concurrent care a factor in whether induction holds.
Frequently Asked Questions
How long should I wait before taking Suboxone?
Short-acting opioids generally require 12 to 24 hours of abstinence, while fentanyl often requires longer because it redistributes from fat stores. Objective withdrawal signs matter more than elapsed hours, which is why clinicians use a COWS score rather than a fixed rule.
What COWS score do I need before induction?
Most protocols require a COWS score of 8 to 12 or higher, and many clinicians prefer 10 to 13 for patients using fentanyl. The score confirms that objective withdrawal is underway and that receptors have cleared enough for safe induction.
How long does precipitated withdrawal last?
Symptoms begin 1 to 2 hours after the triggering dose, peak between hours 2 and 6, and largely resolve within 6 to 24 hours. Residual fatigue and sleep disruption can persist for another day or two.
Can more Suboxone fix precipitated withdrawal?
Yes. Additional buprenorphine is now the standard rescue approach, because saturating mu-opioid receptors ends the partial-occupancy state driving symptoms. This reverses older advice to stop the medication.
What does precipitated withdrawal feel like?
Patients describe the worst withdrawal of their lives arriving within an hour rather than building over days. Vomiting, diarrhea, drenching sweats, deep muscle pain, and an inability to sit still occur simultaneously.
Is precipitated withdrawal the same as normal withdrawal?
No. Precipitated withdrawal results from a medication displacing opioids from receptors and starts abruptly, while spontaneous withdrawal results from opioids clearing naturally and builds over 1 to 3 days. Precipitated withdrawal is shorter but more intense.
What is the Bernese method?
The Bernese method starts buprenorphine at roughly 0.2 to 0.5 mg while the patient continues their full agonist, titrating upward over days. Because each increment is small, receptor displacement happens gradually and no withdrawal spike occurs.
Can Vivitrol cause precipitated withdrawal?
Yes, and more severely than buprenorphine, because naltrexone blocks receptors completely rather than partially. Vivitrol requires full detoxification first, typically 7 or more days after last opioid use.
References
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Publishing.
- American Society of Addiction Medicine. (2020). The ASAM national practice guideline for the treatment of opioid use disorder: 2020 focused update.
- D’Onofrio, G., Hawk, K. F., Perrone, J., Walsh, S. L., Lofwall, M. R., Fiellin, D. A., & Herring, A. A. (2023). Incidence of precipitated withdrawal during a multisite emergency department-initiated buprenorphine clinical trial. JAMA Network Open, 6(3), e236108.
- Florida Department of Law Enforcement, Medical Examiners Commission. (2025). Drugs identified in deceased persons by Florida medical examiners, 2024 annual report.
- Gregory, H., Hemmerlin, K., Woodruff, A., Winograd, R., & Carpenter, R. (2025). Incidence of buprenorphine-precipitated opioid withdrawal in adults with opioid use disorder: A systematic review. Addiction, 120(1), 7-20.
- Hämmig, R., Kemter, A., Strasser, J., von Bardeleben, U., Gugger, B., Walter, M., Dürsteler, K. M., & Vogel, M. (2016). Use of microdoses for induction of buprenorphine treatment with overlapping full opioid agonist use: The Bernese method. Substance Abuse and Rehabilitation, 7, 99-105.
- Substance Abuse and Mental Health Services Administration. (2021). Medications for opioid use disorder (Treatment Improvement Protocol Series 63, Publication No. PEP21-02-01-002).
- Thakrar, A. P., Uritsky, T. J., Christopher, C., Winston, A., Ronan, K., Palladino, N., Levin, S., & Delgado, M. K. (2024). Buprenorphine-precipitated withdrawal among hospitalized patients using fentanyl. JAMA Network Open, 7(9), e2435895.
- Wesson, D. R., & Ling, W. (2003). The Clinical Opiate Withdrawal Scale (COWS). Journal of Psychoactive Drugs, 35(2), 253-259.