
Cannabinoid hyperemesis syndrome is a condition in which long-term cannabis use produces repeated cycles of severe vomiting and abdominal pain. Complete cannabis cessation is the only treatment that resolves it.
The syndrome creates a paradox that confuses patients and clinicians alike. THC relieves nausea at therapeutic doses, yet chronic heavy exposure reverses that effect entirely.
Most people with this syndrome cycle through emergency departments for months before anyone names it. Scans and bloodwork return normal, because the problem sits in receptor signaling rather than in damaged tissue.
Why does hot water help, and how long does recovery actually take?
Key Takeaways
- Complete cannabis cessation is the only treatment that resolves cannabinoid hyperemesis syndrome. Antiemetics, hot showers, and CBD manage symptoms temporarily and do not correct the underlying cause.
- Allen and colleagues first characterized the syndrome in 19 patients in Adelaide, South Australia, published in Gut in 2004, with the index case dating to 1996.
- Compulsive hot bathing appears in roughly 80% to 90% of patients in the review literature and was historically described as near-pathognomonic, meaning it points to this diagnosis more strongly than any other single sign.
- Intravenous haloperidol outperformed ondansetron for acute cannabinoid hyperemesis in the HaVOC randomized controlled trial published in Annals of Emergency Medicine in 2021.
- No verified Florida statistic exists for cannabinoid hyperemesis syndrome specifically. The Florida Department of Health recorded an 836% rise in pediatric marijuana emergency exposures between 2016 and 2023, which serves as a cannabis-availability proxy rather than a measure of this syndrome.
What Is Cannabinoid Hyperemesis Syndrome?
Cannabinoid hyperemesis syndrome (CHS) is a condition in which long-term cannabis use produces cycles of severe vomiting and abdominal pain that resolve only when cannabis use stops completely. Patients characteristically find relief in hot showers and baths.
CHS is a recognized clinical syndrome carrying its own ICD-10 code, not an informal label. It does not appear as a DSM-5-TR diagnosis because DSM-5-TR classifies disorders of behavior rather than physical syndromes, and the underlying condition driving CHS is cannabis use disorder.
The syndrome presents a clinical paradox. THC acts as an antiemetic at therapeutic doses and holds FDA-approved indications for chemotherapy-induced nausea, yet chronic heavy exposure reverses that effect and generates intractable vomiting.
How Cannabinoid Hyperemesis Syndrome Is Diagnosed
CHS diagnosis rests on clinical criteria and exclusion of other causes rather than on a scored instrument or a confirmatory laboratory test. Physicians rule out bowel obstruction, pancreatitis, and pregnancy before assigning the diagnosis.
The clinical features that establish a CHS diagnosis:
- Long-term cannabis use: Weekly or more frequent cannabis use sustained over months to years precedes symptom onset in essentially all documented cases.
- Recurrent cyclic vomiting: Discrete episodes of severe vomiting separate periods of normal or near-normal digestive function.
- Relief with hot bathing: Compulsive hot showering or bathing relieves nausea temporarily, a behavior Simonetto and colleagues documented across a 98-patient Mayo Clinic series in 2012.
- Resolution on cessation: Symptoms resolve after cannabis use stops and return on resumption, which confirms the causal relationship.
Clinicians apply Rome IV criteria for functional gastrointestinal disorders alongside the Simonetto and Sontineni criteria. No blood test or imaging study confirms the diagnosis.
For the underlying substance use disorder, the Cannabis Use Disorders Identification Test-Revised (CUDIT-R) measures cannabis-related harm across 8 items scored 0 to 32. Scores of 8 or above indicate hazardous use, and scores of 12 or above indicate possible cannabis use disorder.
What Causes Cannabinoid Hyperemesis Syndrome?
Chronic THC exposure alters receptor behavior in the gut and brainstem, and inherited variation determines who develops the syndrome. Four causal layers apply.

TRPV1 Receptor Desensitization
Sustained THC exposure desensitizes transient receptor potential vanilloid 1 (TRPV1) receptors in the gastrointestinal tract, disrupting the signaling pathway that regulates nausea and gastric emptying. TRPV1 also mediates heat sensation, which explains the hot-shower phenomenon.
Hot water activates cutaneous TRPV1 receptors and transiently restores signaling in a desensitized system, producing genuine symptom relief. That mechanism links a behavior patients discover accidentally to a specific receptor target, and it is the reason topical capsaicin, a TRPV1 agonist, works as a treatment.
CB1 Receptor Changes in the Gut and Brainstem
Chronic cannabis use downregulates CB1 receptors in the enteric nervous system and the area postrema, the brainstem region that triggers vomiting. Downregulation in the enteric nervous system slows gastric emptying, while altered area postrema signaling lowers the threshold for emesis.
THC also dysregulates the hypothalamic-pituitary-adrenal (HPA) axis, elevating stress hormone output that intensifies gastrointestinal symptoms. Vagus nerve signaling between gut and brainstem carries these disrupted messages in both directions.
Genetic Susceptibility
Ethan Russo and Venetia Whiteley proposed a genetic-susceptibility model in Frontiers in Toxicology in 2024, identifying five significant mutations in patients with CHS. Their findings implicate TRPV1, two dopamine-related genes, cytochrome P450 2C9 (CYP2C9), and an ABC transporter gene.
CYP2C9 variants slow THC metabolism, raising circulating cannabinoid concentrations at any given dose. That model explains why CHS develops in a minority of heavy cannabis users rather than in all of them.
Why Cannabis Use Continues Despite Illness
Patients frequently continue using cannabis during active CHS because THC relieves the anticipatory nausea and anxiety the illness itself generates. That cycle sustains the syndrome and is the mechanism competitor content most often omits.
Cannabis use disorder co-occurs with generalized anxiety disorder because THC produces short-term anxiolytic relief that reinforces repeat dosing. Treating the vomiting without treating the co-occurring anxiety disorder leaves the driver of continued use intact.
The Three Phases of Cannabinoid Hyperemesis Syndrome
CHS progresses through three recognized phases that differ in duration, symptom profile, and treatment response. The phases repeat in cycles until cannabis use stops.
- Prodromal phase, months to years: Early morning nausea, vague abdominal discomfort, and fear of vomiting appear while eating patterns remain largely normal. Many patients increase cannabis use during this phase to treat the nausea, which accelerates progression.
- Hyperemetic phase, 24 to 48 hours per episode: Intense, repeated vomiting begins, frequently 5 or more times per hour, accompanied by diffuse abdominal pain and compulsive hot bathing. Emergency department presentation concentrates in this phase, and dehydration develops rapidly.
- Recovery phase, days to months: Vomiting stops, appetite returns, and weight recovers after cannabis cessation. Full gastrointestinal normalization commonly requires 1 to 3 months of complete abstinence, and resuming cannabis returns patients to the hyperemetic phase.
Recovery duration is the detail patients most often misunderstand. Symptom relief within days of cessation does not indicate resolution, and receptor recovery continues for weeks after vomiting stops.
Cannabinoid Hyperemesis Syndrome Symptoms by Severity
CHS symptoms range from the mild prodromal nausea patients tolerate for years to complications that threaten organ function. Symptoms sort into three tiers.
Common Symptoms
Symptoms present in most CHS presentations:
- Cyclic vomiting: Repeated forceful vomiting occurs in discrete episodes, which patients and online communities call scromiting when screaming accompanies the retching.
- Diffuse abdominal pain: Visceral hypersensitivity generates cramping pain across the upper abdomen rather than at one localized point.
- Compulsive hot bathing: Patients take prolonged hot showers many times daily because cutaneous TRPV1 activation relieves nausea.
- Morning nausea: Nausea concentrates on waking, before any cannabis use that day, distinguishing it from acute intoxication effects.
- Weight loss and appetite suppression: Repeated vomiting and food avoidance drive unintentional weight loss over successive episodes.
Severe Symptoms and Emergency Complications
CHS is not directly lethal, but its complications endanger kidney function, cardiac rhythm, and the esophagus. Recognizing the emergency threshold prevents organ injury.
Complications that require emergency evaluation:
- Severe dehydration and hypovolemia: Sustained vomiting depletes intravascular volume, producing tachycardia, hypotension, and dizziness on standing.
- Hypokalemia and electrolyte derangement: Vomiting depletes potassium, and hypokalemia generates cardiac arrhythmias and muscle weakness.
- Acute kidney injury: Volume depletion reduces renal perfusion and produces what clinicians term cannabinoid hyperemesis acute renal failure.
- Esophageal injury: Forceful repeated vomiting tears esophageal mucosa, producing Mallory-Weiss tears and, rarely, full-thickness rupture.
- Hot water burns: Compulsive bathing at escalating temperatures produces scald injuries, a complication documented across multiple case series.
Seek emergency care immediately for any of the following: inability to keep fluids down for more than 12 hours, blood in vomit, chest pain, fainting, confusion, or no urine output for 8 hours or longer. Intravenous rehydration and electrolyte correction cannot be accomplished at home.
Long-Term Risks
Consequences that accumulate across repeated CHS cycles:
- Progressive malnutrition: Repeated hyperemetic episodes deplete thiamine and other micronutrients, producing fatigue and cognitive impairment.
- Dental erosion: Gastric acid contacting tooth enamel during repeated vomiting produces irreversible erosion.
- Escalating cannabis use disorder: Using cannabis to treat CHS nausea deepens dependence and shortens the interval between episodes.
- Diagnostic delay and repeat hospitalization: Patients average multiple emergency visits and extensive negative workups before receiving the correct diagnosis.
CHS vs Cyclic Vomiting Syndrome and Gastroparesis
CHS shares its central symptom with two other conditions, and distinguishing among them determines the entire treatment pathway. Cannabis history and the hot-bathing pattern are the decisive features.
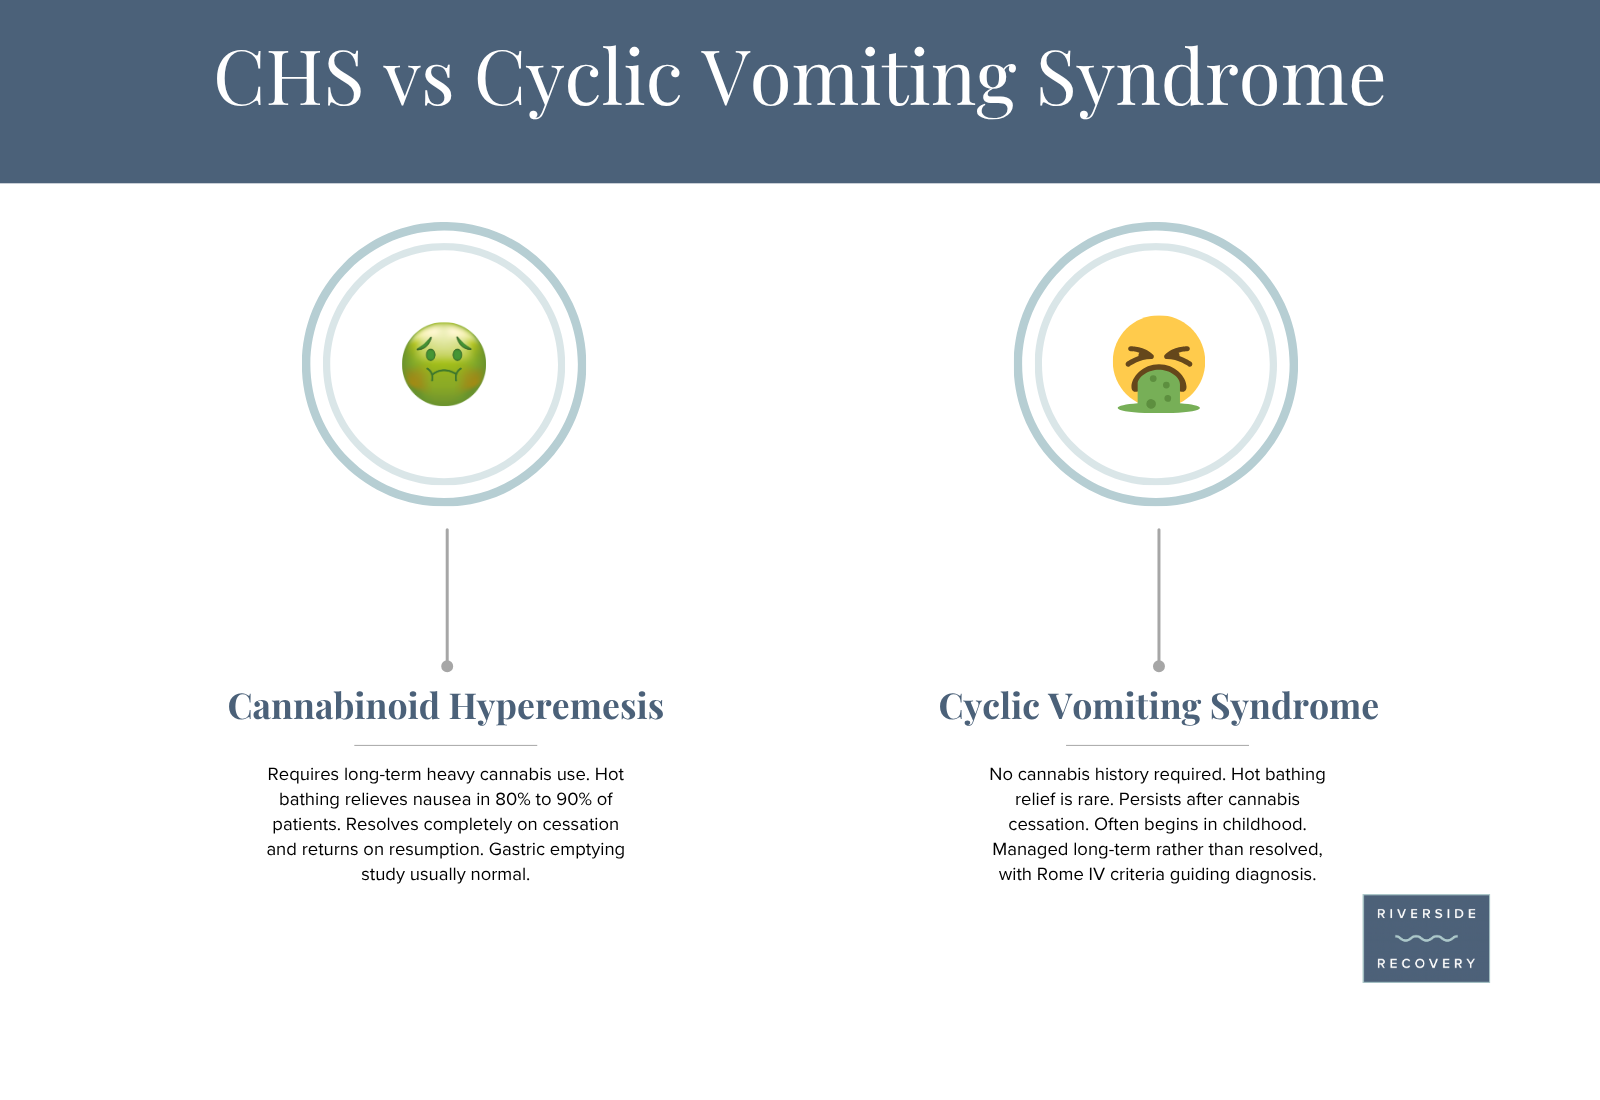
| Feature | Cannabinoid hyperemesis syndrome | Cyclic vomiting syndrome | Gastroparesis |
|---|---|---|---|
| Cannabis history | Long-term heavy use, always present | Not required | Not required |
| Hot bathing relief | Present in 80% to 90% | Rare | Absent |
| Symptom pattern | Discrete episodes with well periods | Discrete episodes with well periods | Continuous, meal-related |
| Response to cessation | Resolves completely | No change | No change |
| Gastric emptying study | Usually normal | Usually normal | Delayed, confirms diagnosis |
| Typical age of onset | Adults in their twenties and thirties | Often childhood onset | Any age, frequently with diabetes |
Cyclic vomiting syndrome mirrors the episodic pattern of CHS but persists after cannabis cessation. Gastroparesis produces continuous meal-related symptoms and shows delayed gastric emptying on scintigraphy, whereas CHS gastric emptying studies typically return normal.
Treatment for Cannabinoid Hyperemesis Syndrome
CHS treatment separates into acute episode management and definitive resolution through cessation. Four tiers apply.
First-Line: Cannabis Cessation and Behavioral Therapy
Complete cannabis cessation is the only intervention that resolves CHS permanently, which makes cannabis use disorder treatment the definitive therapy rather than an adjunct. Partial reduction does not produce resolution.
Therapies that support sustained cannabis cessation:
- Cognitive behavioral therapy (CBT): CBT identifies the situational cues and thought patterns preceding cannabis use and installs rehearsed alternatives.
- Contingency management: Verified incentives for cannabis-negative urine screens produce the largest effect sizes of any cannabis use disorder intervention.
- Motivational enhancement therapy: Motivational interviewing resolves the ambivalence CHS patients feel when cannabis both causes and temporarily relieves their symptoms.
Pharmacological Management of Acute Episodes
Standard antiemetics perform poorly in acute CHS, and dopamine antagonists outperform serotonin antagonists. Medication choice differs from routine vomiting protocols.
Medications used for the hyperemetic phase:
- Haloperidol: Intravenous haloperidol, a dopamine D2 antagonist, outperformed ondansetron in the HaVOC randomized controlled trial published in Annals of Emergency Medicine in 2021. Haloperidol requires baseline electrocardiography because it prolongs the QTc interval.
- Droperidol: Droperidol produces similar benefit to haloperidol through the same dopamine antagonism and carries the same QTc monitoring requirement.
- Ondansetron: Ondansetron, a 5-HT3 antagonist, remains widely administered despite underperforming dopamine antagonists in head-to-head comparison.
- Intravenous fluids and electrolyte repletion: Volume resuscitation and potassium correction address the complications that actually threaten organ function.
Second-Line and Adjunct Treatments
Additional options when first-line management proves insufficient:
- Topical capsaicin cream: Capsaicin 0.025% to 0.075% applied to the abdomen activates TRPV1 receptors and reproduces the mechanism of hot bathing. The American Gastroenterological Association endorsed capsaicin as a first-line adjunct in its 2024 clinical practice update.
- Benzodiazepines: Lorazepam reduces the anticipatory anxiety and agitation that accompany severe episodes, prescribed short-term only.
- Dialectical behavior therapy (DBT): DBT builds distress tolerance for patients whose cannabis use functions as emotion regulation.
Emerging and Investigational Treatments
Treatments under investigation for cannabinoid hyperemesis syndrome:
- Olanzapine: Olanzapine offers dopamine antagonism with lower QTc risk than haloperidol, supported by limited evidence and used off-label.
- Aprepitant and fosaprepitant: These neurokinin-1 antagonists target a separate emetic pathway and remain investigational for CHS.
- Genetic screening: The Russo and Whiteley 2024 susceptibility model raises the prospect of identifying at-risk cannabis users before symptom onset, currently a research application rather than a clinical test.
Two widely circulated online claims are false. Neither cannabidiol (CBD) nor increased cannabis use cures CHS, and both prolong the syndrome by sustaining cannabinoid exposure.
Cessation is the only curative intervention, a position the National Institute on Drug Abuse research literature supports. Advice found in forums recommending more cannabis reverses the treatment.
Treatment at Riverside Recovery of Tampa
Riverside Recovery of Tampa treats adults 18 and older for substance use disorders and co-occurring mental health conditions across a full continuum of care. The 60,000-square-foot waterfront facility sits on the Hillsborough River near downtown Tampa and has operated since 2017.
The Joint Commission accredits Riverside Recovery, and CARF International accredits the facility at American Society of Addiction Medicine (ASAM) Level 3.5 for residential treatment. Riverside Recovery also carries LegitScript certification and belongs to the National Association of Addiction Treatment Providers.
The Florida Department of Children and Families and the Agency for Health Care Administration license the facility. Riverside Recovery has operated under those licenses since 2017.
“Patients with cannabinoid hyperemesis have usually been told repeatedly that their scans are normal, which leaves them convinced no one can explain what is happening,” says Dr. Michael Sore, MD, Medical Director at Riverside Recovery of Tampa. “Naming the syndrome and connecting it to cannabis is often the first time the picture makes sense to them.”

Medical Detoxification
Riverside Recovery provides 24-hour medically supervised medical detox overseen by Dr. Michael Sore, MD, alongside the nursing and clinical team. Vital signs receive around-the-clock monitoring, and cannabis withdrawal receives protocols calibrated to individual presentation rather than a standard applied across substances.
Residential Treatment
Residential treatment at ASAM Level 3.5 removes access to cannabis during the weeks when receptor recovery begins, which is the period patients most often relapse through when attempting cessation at home. Programming includes CBT, DBT, motivational interviewing, mindfulness-based relapse prevention, trauma resolution therapy, and Accelerated Resolution Therapy (ART).
Dual Diagnosis Care
Riverside Recovery treats co-occurring mental health conditions concurrently with substance use disorders rather than in sequence. For CHS patients, addressing the anxiety that drives continued use determines whether cessation holds after discharge.
Intensive Outpatient and Outpatient Programming
The intensive outpatient program, day/night partial hospitalization, and standard outpatient therapy extend clinical contact through the 1-to-3-month window when gastrointestinal function normalizes. Patients move between levels without changing facilities or clinical teams.
Frequently Asked Questions
Why do hot showers help cannabinoid hyperemesis syndrome?
Hot water activates TRPV1 receptors in the skin, temporarily restoring signaling in a receptor system that chronic THC exposure has desensitized. The relief is genuine but lasts only while the skin stays hot, which is why patients bathe compulsively.
How long does CHS recovery take after quitting cannabis?
Vomiting typically stops within days of complete cessation, while full gastrointestinal normalization requires 1 to 3 months. Appetite and weight recover gradually across that period, and any return to cannabis restarts the hyperemetic phase.
Does cannabinoid hyperemesis syndrome go away?
Yes, CHS resolves completely with permanent cannabis cessation. It is not a chronic condition requiring lifelong management, but it returns reliably on resuming cannabis, which makes sustained abstinence the treatment rather than a recommendation.
Does capsaicin cream work for CHS?
Topical capsaicin at 0.025% to 0.075% applied to the abdomen relieves acute nausea by activating the same TRPV1 receptors that hot water targets. The American Gastroenterological Association endorsed it as a first-line adjunct in 2024.
Can occasional cannabis smokers get CHS?
CHS develops almost exclusively after months to years of weekly or more frequent use. Genetic variation in CYP2C9 and TRPV1 determines susceptibility, so heavy use raises risk without guaranteeing the syndrome.
Can you get CHS from edibles?
Yes. CHS results from cumulative cannabinoid exposure rather than from combustion, so edibles, vaporized concentrates, and smoked flower all produce it. Route of administration does not protect against the syndrome.
Is CHS the same as cyclic vomiting syndrome?
No. Both produce episodic vomiting with symptom-free intervals, but CHS requires a heavy cannabis history and resolves on cessation. Cyclic vomiting syndrome persists regardless of cannabis use and often begins in childhood.
What is scromiting?
Scromiting combines screaming and vomiting and describes the retching accompanied by cries of pain that characterizes severe hyperemetic episodes. It is patient and online community terminology, not a clinical term, and describes a symptom rather than a separate condition.
References
- Allen, J. H., de Moore, G. M., Heddle, R., & Twartz, J. C. (2004). Cannabinoid hyperemesis: Cyclical hyperemesis in association with chronic cannabis abuse. Gut, 53(11), 1566-1570.
- Adamson, S. J., Kay-Lambkin, F. J., Baker, A. L., Lewin, T. J., Thornton, L., Kelly, B. J., & Sellman, J. D. (2010). An improved brief measure of cannabis misuse: The Cannabis Use Disorders Identification Test-Revised (CUDIT-R). Drug and Alcohol Dependence, 110(1-2), 137-143.
- American Gastroenterological Association. (2024). AGA clinical practice update on the medical management of cannabinoid hyperemesis syndrome. Gastroenterology.
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Publishing.
- Ruberto, A. J., Sivilotti, M. L. A., Forrester, S., Hall, A. K., Crawford, F. M., & Day, A. G. (2021). Intravenous haloperidol versus ondansetron for cannabis hyperemesis syndrome (HaVOC): A randomized, controlled trial. Annals of Emergency Medicine, 77(6), 613-619.
- Russo, E. B., & Whiteley, V. L. (2024). Cannabinoid hyperemesis syndrome: Genetic susceptibility to toxic exposure. Frontiers in Toxicology, 6, 1465728.
- Simonetto, D. A., Oxentenko, A. S., Herman, M. L., & Szostek, J. H. (2012). Cannabinoid hyperemesis: A case series of 98 patients. Mayo Clinic Proceedings, 87(2), 114-119.
- Sontineni, S. P., Chaudhary, S., Sontineni, V., & Lanspa, S. J. (2009). Cannabinoid hyperemesis syndrome: Clinical diagnosis of an underrecognised manifestation of chronic cannabis abuse. World Journal of Gastroenterology, 15(10), 1264-1266.
- Florida Department of Health. (2024, October 22). Guidance for non-medical marijuana use in adolescents. State Surgeon General.
- National Institute on Drug Abuse. (2024). Cannabis (marijuana) research report. National Institutes of Health.