




Yes, Roxicodone and oxycodone are the same drug: Roxicodone is the brand name for immediate-release oxycodone hydrochloride tablets, and generic oxycodone IR contains the same active ingredient at the same strength and potency.
Roxicodone is a brand name for immediate-release oxycodone HCl tablets in 5mg, 15mg, and 30mg strengths. Generic oxycodone encompasses the same immediate-release formulation plus extended-release (OxyContin) and combination products containing acetaminophen (Percocet).
Key Takeaways
- Roxicodone is a brand name for immediate-release oxycodone hydrochloride; it and generic oxycodone IR contain the same active ingredient at the same pharmacological potency.
- The United States recorded 107,941 drug overdose deaths in 2022, according to the Centers for Disease Control and Prevention. Most involved synthetic opioids, a category that means illicitly made fentanyl and its analogues rather than prescription oxycodone, which is a semi-synthetic opioid counted separately.
- Oxycodone is approximately 1.5 times more potent than morphine by equianalgesic dose; it is less potent than hydromorphone, oxymorphone, and fentanyl.
- In 2022, 3.7% of US adults, about 9.4 million people, needed treatment for opioid use disorder, and only 25.1% of them received medication for it.
- The DEA classifies all oxycodone formulations, including Roxicodone, as Schedule II controlled substances, reflecting high abuse potential and a narrow therapeutic-to-misuse window.
What Is Roxicodone?
Roxicodone is the brand name for an immediate-release oxycodone hydrochloride tablet, available in 5mg, 15mg, and 30mg strengths, indicated for the management of moderate to severe acute pain where around-the-clock dosing is not required.
Roxicodone as a Brand Name
Roxicodone was originally developed by Xanodyne Pharmaceuticals and subsequently licensed to other manufacturers. The formulation contains no acetaminophen, no acetylsalicylic acid, and no other secondary analgesic compound. Its active pharmaceutical ingredient is oxycodone hydrochloride, the same compound present in generic oxycodone IR tablets, Percocet, OxyContin, and Oxaydo. Roxicodone’s brand-name status confers no pharmacological advantage over generic immediate-release oxycodone HCl; both produce identical mu-opioid receptor binding kinetics and identical onset and duration profiles.
Roxicodone Available Strengths and DEA Status
Roxicodone is manufactured in three tablet strengths covering the full immediate-release oxycodone dosage range most commonly used in clinical practice.
- Roxicodone 5mg: Round, white tablet; oxycodone HCl 5mg; lowest immediate-release starting dose for opioid-naive patients per ASAM pain management guidelines
- Roxicodone 15mg: Round, green tablet; oxycodone HCl 15mg; intermediate dose for partial opioid tolerance
- Roxicodone 30mg: Round, blue tablet; oxycodone HCl 30mg; highest Roxicodone strength; visually similar to counterfeit M30 pills containing illicitly manufactured fentanyl
- DEA Schedule II: High abuse potential, currently accepted medical use with severe restrictions, and potential for severe psychological or physical dependence
What Is Oxycodone and How Do Its Formulations Differ?
Oxycodone is a semi-synthetic opioid pain medicine made from thebaine, a compound in the opium poppy, and it is the active ingredient in Roxicodone, generic oxycodone IR, Percocet and OxyContin.

Immediate-Release Oxycodone HCl
Immediate-release oxycodone HCl includes both Roxicodone and its generic equivalents. These formulations deliver the full dose rapidly into systemic circulation, producing peak plasma concentrations within 1 to 2 hours of ingestion. Immediate-release oxycodone provides analgesia for 4 to 6 hours per dose, making it suitable for acute pain management but presenting higher misuse risk per dose compared to extended-release formats due to the rapid onset of euphoric reward effects that NIDA Director Dr. Nora Volkow’s neurobiological research identifies as the primary driver of dopaminergic reinforcement in opioid use disorder development.
Extended-Release Oxycodone (OxyContin)
OxyContin contains oxycodone HCl in a polymer matrix designed to release the drug over 12 hours, delivering therapeutic concentrations with reduced peak-to-trough fluctuation. OxyContin was developed by Purdue Pharma in 1996 and contributes directly to the initiation of the opioid epidemic through aggressive marketing of extended-release formulations for non-cancer pain. The abuse-deterrent formulation introduced in 2010 replaced the original OxyContin, partially reducing injection misuse but not oral misuse of crushed tablets.
Oxycodone-Acetaminophen Combinations (Percocet)
Percocet combines oxycodone HCl with acetaminophen 325mg in a single immediate-release tablet. The acetaminophen component provides synergistic analgesia via central prostaglandin inhibition and theoretically deters escalating misuse by introducing hepatotoxic risk at high doses. Available in 2.5mg, 5mg, 7.5mg, and 10mg oxycodone strengths, Percocet is the most prescribed opioid-acetaminophen combination in the United States.
How Do Roxicodone and Other Oxycodone Products Compare?
Roxicodone, generic oxycodone IR, Percocet and OxyContin all contain oxycodone hydrochloride, but they differ in release speed, duration, available strengths and whether acetaminophen is added to the tablet.
| Feature | Roxicodone | Generic Oxycodone IR | Percocet | OxyContin |
|---|---|---|---|---|
| Active ingredient | Oxycodone HCl | Oxycodone HCl | Oxycodone HCl + APAP 325mg | Oxycodone HCl |
| Formulation type | Immediate-release | Immediate-release | Immediate-release | Extended-release |
| Onset of action | 10 to 30 minutes | 10 to 30 minutes | 10 to 30 minutes | 1 to 2 hours |
| Duration of analgesia | 4 to 6 hours | 4 to 6 hours | 4 to 6 hours | 12 hours |
| Available strengths | 5mg, 15mg, 30mg | 5mg, 10mg, 15mg, 20mg, 30mg | 2.5mg, 5mg, 7.5mg, 10mg | 10 to 80mg |
| Acetaminophen | None | None | 325mg per tablet | None |
| DEA Schedule | Schedule II | Schedule II | Schedule II | Schedule II |
| Abuse potential | High (rapid onset) | High (rapid onset) | High (rapid onset) | High (abuse-deterrent reformulation) |

How Does Oxycodone Work in the Brain?
Oxycodone works by attaching to mu-opioid receptors in the brain and spinal cord, which blocks pain, causes drowsiness and releases dopamine in the brain’s reward center, the effect that drives addiction.
Mu-Opioid Receptor Binding Mechanism
Oxycodone binds mu-opioid receptors (MOR) in the periaqueductal gray, dorsal horn of the spinal cord, and medullary respiratory center, producing three simultaneous pharmacological effects that explain both its analgesic utility and overdose risk. MOR activation in the ventral tegmental area drives dopamine release into the nucleus accumbens, producing the euphoric reward signal that initiates conditioned drug-seeking behavior. MOR activation in the medullary respiratory center suppresses the hypercapnic ventilatory drive, the primary mechanism of fatal opioid respiratory depression. Oxycodone binds MOR with approximately 1.5 times the affinity of morphine, making it more potent per milligram than the benchmark opioid comparator.
Hepatic Metabolism via CYP3A4 and CYP2D6
Oxycodone undergoes hepatic first-pass metabolism primarily through the cytochrome P450 CYP3A4 pathway, which converts it to the inactive metabolite noroxycodone, and secondarily through CYP2D6, which converts it to oxymorphone, an active metabolite with higher MOR binding affinity than the parent compound. CYP2D6 polymorphisms produce clinically significant variability in oxycodone response: ultra-rapid metabolizers convert a larger fraction to oxymorphone, increasing analgesic and euphoric effects; poor metabolizers produce less oxymorphone, reducing efficacy and potentially reducing abuse liability in this genotype. Drug interactions with CYP3A4 inhibitors such as ketoconazole, erythromycin, and grapefruit juice increase oxycodone plasma concentrations and overdose risk by blocking the primary elimination pathway.
Is Roxicodone Stronger than Other Opioids?
Roxicodone sits in the middle of the opioid strength range: it is stronger than codeine and hydrocodone, about 1.5 times as strong as oral morphine, and weaker than hydromorphone, oxymorphone and fentanyl.
Roxicodone vs. Hydrocodone
Oxycodone is approximately 1.5 times more potent than hydrocodone by equianalgesic dose. Oxycodone 10mg produces approximately equivalent analgesia to hydrocodone 15mg. Both bind mu-opioid receptors as full agonists. Both carry DEA Schedule II classification following the reclassification of hydrocodone combination products from Schedule III in 2014. Clinical studies comparing abuse potential show higher diversion rates for oxycodone relative to hydrocodone, attributed to oxycodone’s higher MOR binding affinity and more pronounced dopaminergic reward signal at equivalent therapeutic doses.
Roxicodone vs. Morphine and the Equianalgesic Table
Standard equianalgesic conversion ratios used in palliative care and pain management position oxycodone at 1.5 times oral morphine potency. The clinical implication is that oral oxycodone 10mg provides analgesia equivalent to oral morphine 15mg. On the standard oral equianalgesic table, 30mg of oral morphine is equivalent to 20mg oxycodone, 7.5mg hydromorphone and 10mg oxymorphone. That places hydromorphone at roughly 4 times oral morphine potency and oxymorphone at roughly 3 times. Hydromorphone’s often-quoted 5 to 8 times figure describes the injectable route, not tablets. Fentanyl is 50 to 100 times more potent than morphine, explaining why a counterfeit Roxicodone tablet containing illicitly manufactured fentanyl presents a categorical overdose risk far exceeding any legitimate oxycodone formulation.
When Opioid Use Disorder Risk Begins
Physical dependence to oxycodone develops within 2 to 4 weeks of daily therapeutic use in most patients, reflecting neuroadaptive downregulation of mu-opioid receptor density and uncoupling of MOR from its G-protein signaling cascade. Physical dependence is not the same as oxycodone addiction, which DSM-5-TR calls opioid use disorder. DSM-5-TR opioid use disorder requires a pattern of compulsive drug-seeking behavior, loss of control over use, and continued use despite clinically significant harm, regardless of whether use began with a legitimate prescription. The Clinical Opiate Withdrawal Scale (COWS) provides standardized measurement of opioid withdrawal severity across 11 parameters, generating scores from 5 to 12 (mild), 13 to 24 (moderate), 25 to 36 (moderately severe), and above 36 (severe), which guide buprenorphine induction timing and dose escalation in clinical detoxification protocols.
How Is Opioid Use Disorder Diagnosed?
Opioid use disorder is diagnosed when a person meets at least 2 of the 11 DSM-5-TR criteria within 12 months, whether the opioid was a legitimate Roxicodone prescription or a counterfeit pill.
- Tolerance and dose escalation: A clear increase in the amount of oxycodone needed to reach the desired effect, or a much weaker effect from the same amount
- Withdrawal-driven use: Oxycodone is taken to relieve or avoid withdrawal symptoms including anxiety, myalgia, diaphoresis, and gastrointestinal distress
- Loss of control: Taking oxycodone in larger amounts or over a longer period than intended despite intentions to limit use
- Unsuccessful reduction attempts: Persistent desire or unsuccessful efforts to cut down or control oxycodone use
- Time preoccupation: Significant time spent obtaining, using, or recovering from the effects of oxycodone
- Craving: Strong urge or desire to use oxycodone, frequently experienced as intrusive, difficult to suppress, and triggered by drug-associated environmental cues
- Role failure: Recurrent oxycodone use resulting in failure to fulfill major role obligations at work, school, or home
How Does Riverside Recovery of Tampa Treat Opioid Use Disorder?
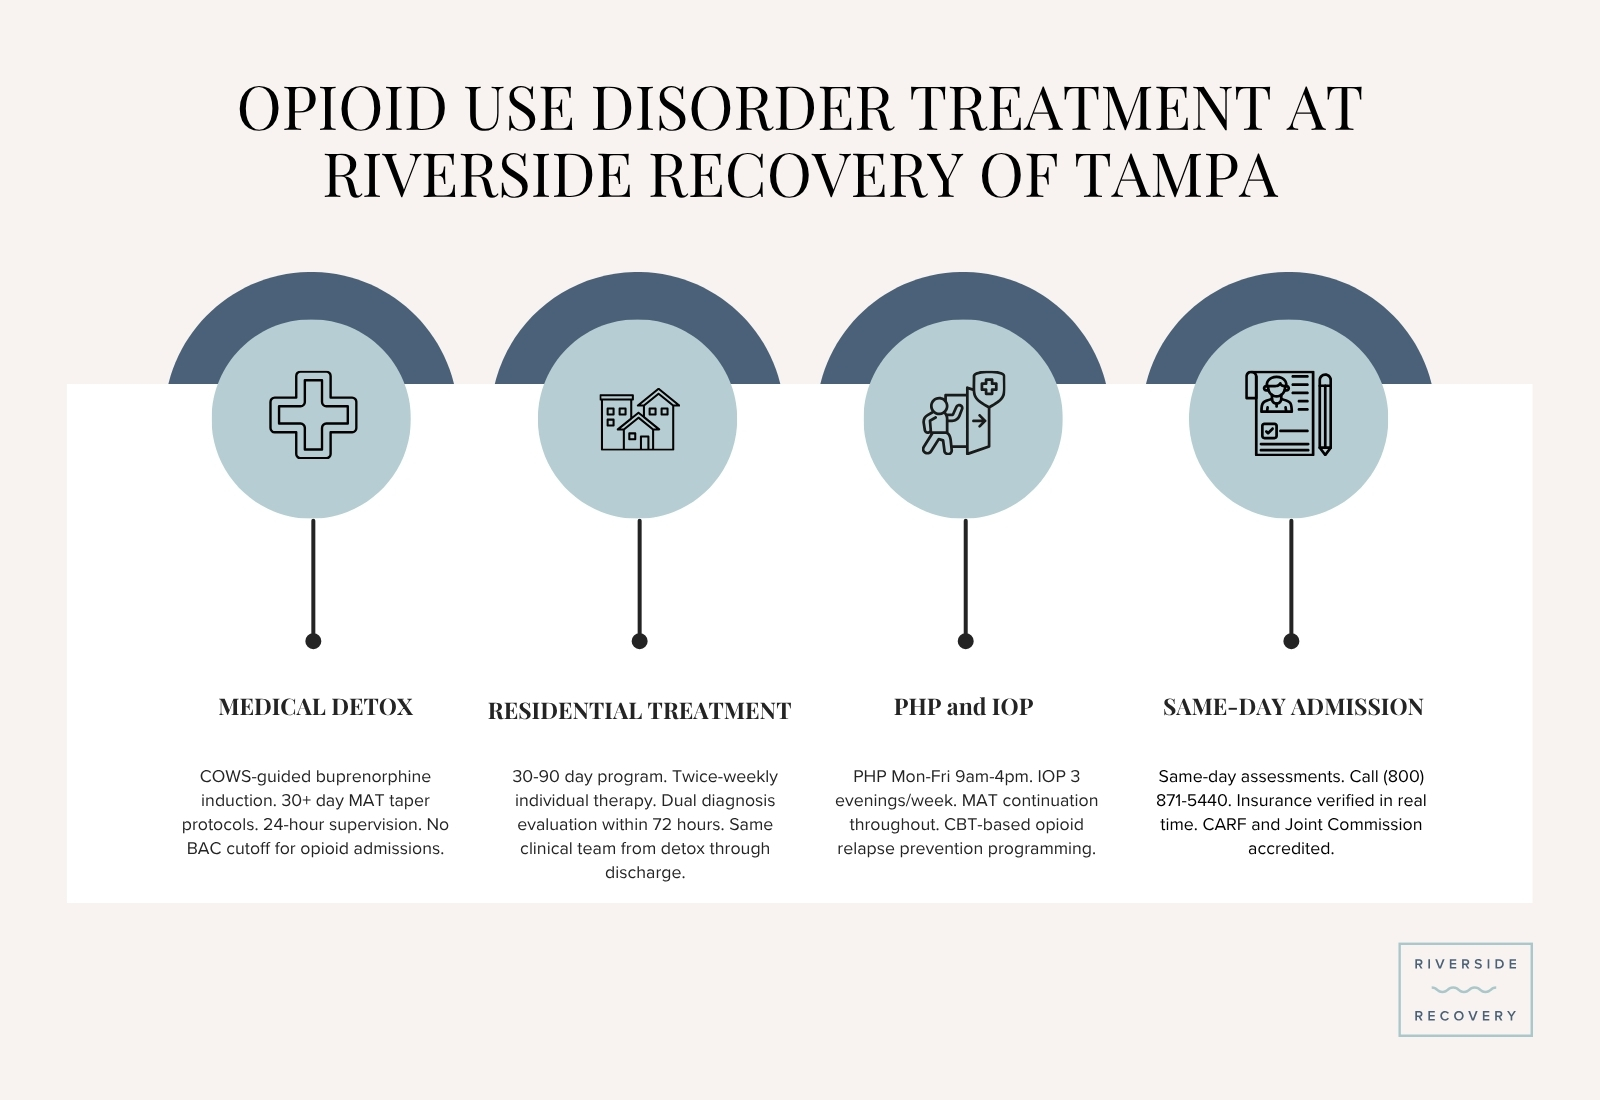
Riverside Recovery of Tampa treats oxycodone and Roxicodone use disorder with COWS-guided medical detox, then residential and step-down care run by the same clinical team at every level.
Treatment addresses both physical dependence and the behavioral, cognitive and co-occurring psychiatric factors that keep compulsive opioid use going.
Medical Detox for Oxycodone Dependence
Riverside Recovery’s medication-assisted treatment (MAT) unit administers buprenorphine/naloxone and methadone under 24-hour supervision by a five-provider medical team.
Buprenorphine tapering at Riverside Recovery is managed under ASAM Level 3.7 medically monitored inpatient care standards, with the pace set from each patient’s dose, duration of use and withdrawal history. No BAC cutoff applies to opioid admissions. The facility handles medically complex opioid patients including those with hepatitis C co-infection, opioid-induced GI dysmotility, and polysubstance co-dependence involving oxycodone and benzodiazepines.
Residential Treatment
Residential treatment provides 24-hour structured care on the Hillsborough River campus for 30 to 90 days under ASAM Level 3.5 clinically managed high-intensity residential criteria. Twice-weekly individual therapy sessions, daily group therapy incorporating CBT-based relapse prevention and DBT skills training, and DSM-5-TR-informed dual diagnosis evaluation begin within the first 72 hours of residential admission.
A systematic review and meta-analysis of mental disorders among people with opioid use disorder recorded current depression in 36.1% and current anxiety in 29.1%. In treatment-seeking populations specifically, current major depressive disorder runs between 20% and 30%. Shared mesolimbic dopaminergic dysregulation is one mechanism implicated in that overlap. Riverside Recovery conducts psychiatric evaluations during residential intake to identify co-occurring conditions requiring concurrent pharmacological and psychotherapeutic management alongside opioid use disorder treatment.
Day/Night Treatment and Intensive Outpatient
Evidence-based addiction therapy continues through PHP (Monday through Friday, 9am to 4pm) and IOP (Monday, Tuesday, Thursday, 6pm to 9pm). All outpatient levels include MAT continuation, random urine drug screening, structured 12-step participation with sponsor engagement, and CBT-based relapse prevention addressing oxycodone-specific environmental cue triggers and prescription drug craving patterns. Virtual IOP is available for patients requiring remote access. All treatment programs are covered by most major private insurance, with benefits verified in real time at admission.
If someone may be overdosing on oxycodone: call 911 at once for slow or stopped breathing, blue or gray lips, or if you cannot wake them, and give naloxone (Narcan) if you have it. For a mental health or substance use crisis, the 988 Suicide and Crisis Lifeline takes calls, texts and online chat at 988lifeline.org 24 hours a day, in English and Spanish, with ASL videophone support for Deaf and hard of hearing callers.
Riverside Recovery of Tampa treats opioid use disorder, including oxycodone use disorder, with medical detox and medication-assisted treatment, and its admissions line at (800) 871-5440 is staffed 24 hours a day. The Riverside Recovery of Tampa admissions page explains the phone screening, what to have ready and when same-day intake is possible.
Frequently Asked Questions
Are Percocet and Roxicodone the same?
No. Both contain oxycodone HCl as the active ingredient, but Percocet adds acetaminophen 325mg per tablet and is available in strengths up to 10mg oxycodone. Roxicodone contains only oxycodone HCl with no secondary compound, and is available in higher strengths (15mg and 30mg) not found in Percocet. Both are DEA Schedule II immediate-release opioids with identical abuse potential.
Is Roxicodone stronger than hydrocodone?
Yes. Oxycodone is approximately 1.5 times more potent than hydrocodone on an equianalgesic basis. Oxycodone 10mg provides roughly equivalent analgesia to hydrocodone 15mg. Both bind mu-opioid receptors as full agonists. Both are DEA Schedule II. Clinical data shows higher rates of non-medical use for oxycodone relative to hydrocodone, attributed to oxycodone’s stronger dopaminergic reward signal at equivalent therapeutic doses.
What is stronger than oxycodone?
Hydromorphone (Dilaudid) is roughly 4 times more potent than oral morphine and roughly 2.7 times more potent than oxycodone on the oral equianalgesic table, where 7.5mg hydromorphone matches 20mg oxycodone. Oxymorphone (Opana) is 3 times more potent than morphine and approximately 2 times more potent than oxycodone. Fentanyl is 50 to 100 times more potent than morphine. Carfentanil, a veterinary sedative not approved for human use, is approximately 10,000 times more potent than morphine.
What are the top 5 strongest prescription opioids?
Ranked by equianalgesic potency relative to oral morphine: (1) Fentanyl patches and lozenges (50 to 100x morphine); (2) Hydromorphone/Dilaudid (about 4x oral morphine, 5 to 8x when injected); (3) Oxymorphone/Opana (3x morphine); (4) Methadone (variable, 5 to 10x morphine at higher doses); (5) Oxycodone/Roxicodone (1.5x morphine). All five are DEA Schedule II with high abuse potential and narrow therapeutic-to-lethal dose margins.
What is the difference between Roxicodone and oxycodone HCl?
None pharmacologically. Roxicodone is a brand name; oxycodone HCl is the generic name for the same compound. Both contain oxycodone hydrochloride in identical immediate-release tablet formulations. Generic oxycodone IR offers more strength options (including 10mg and 20mg tablets) than the Roxicodone brand, which is limited to 5mg, 15mg, and 30mg. Cost, availability, and manufacturer identity are the only practical differences.
Does Roxicodone show up on a drug test?
Yes. Oxycodone, including Roxicodone, is detected on standard urine drug screens. Most immunoassay screens include an oxycodone-specific panel separate from the general opiate screen, because oxycodone’s structure differs enough from morphine that standard opiate tests may not reliably detect it. Confirmatory GC-MS or LC-MS/MS testing quantifies oxycodone, noroxycodone, and oxymorphone metabolites. Detection window is approximately 2 to 4 days in urine for therapeutic doses.
Is Roxicodone the same as OxyContin?
Both contain oxycodone HCl, but they are not the same product. Roxicodone is an immediate-release formulation with a 4 to 6-hour duration; OxyContin is an extended-release formulation designed to last 12 hours. Their onset, duration and misuse risk profiles differ. OxyContin’s higher single-dose oxycodone content (10 to 80mg) and extended release mechanism drove a distinct pattern of extraction and injection misuse during the early opioid epidemic that Roxicodone’s lower-dose immediate-release format does not replicate.
Can someone develop opioid use disorder from a legitimate Roxicodone prescription?
Yes. DSM-5-TR opioid use disorder can develop from any regular opioid exposure, including legitimate prescriptions. Physical dependence develops within 2 to 4 weeks of daily oxycodone use. Whether dependence progresses to opioid use disorder depends on neurobiological vulnerability, genetic factors including MOR gene (OPRM1) variants, co-occurring psychiatric conditions, and duration of exposure. Prescription origin does not reduce disorder risk once neuroadaptive mu-opioid receptor downregulation occurs.
References
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Publishing.
- American Society of Addiction Medicine. (2020). The ASAM clinical practice guideline on alcohol, stimulant, or benzodiazepine withdrawal management. ASAM.
- Centers for Disease Control and Prevention, National Center for Health Statistics. (2023). Drug overdose deaths in the United States, 2001-2022 (NCHS Data Brief No. 491).
- Dowell, D., Brown, S., Gyawali, S., Hoenig, J., Ko, J., Mikosz, C., Ussery, E., Baldwin, G., Jones, C. M., Olsen, Y., Tomoyasu, N., Han, B., Compton, W. M., & Volkow, N. D. (2024). Treatment for opioid use disorder: Population estimates, United States, 2022. MMWR Morbidity and Mortality Weekly Report, 73(25), 567-574.
- Drug Enforcement Administration. (2023). National drug threat assessment 2023. U.S. Department of Justice.
- National Institute on Drug Abuse. (n.d.). Drug overdose death rates. https://nida.nih.gov/research-topics/trends-statistics/overdose-death-rates
- Santo, T., Jr., Campbell, G., Gisev, N., Martino-Burke, D., Wilson, J., Colledge-Frisby, S., Clark, B., Tran, L. T., & Degenhardt, L. (2022). Prevalence of mental disorders among people with opioid use disorder: A systematic review and meta-analysis. Drug and Alcohol Dependence, 238, 109551.
- Smith, H. S. (2009). Opioid metabolism. Mayo Clinic Proceedings, 84(7), 613-624.
- Substance Abuse and Mental Health Services Administration. (2023). National Survey on Drug Use and Health, 2022 results. U.S. Department of Health and Human Services.
- Volkow, N. D., & McLellan, A. T. (2016). Opioid abuse in chronic pain: Misconceptions and mitigation strategies. New England Journal of Medicine, 374(13), 1253-1263.
- Weiss, R. D., Potter, J. S., Fiellin, D. A., Byrne, M., Connery, H. S., Dickinson, W., Gardin, J., Griffin, M. L., Gourevitch, M. N., Haller, D. L., Hasson, A. L., Huang, Z., Jacobs, P., Kosinski, A. S., Lindblad, R., McCance-Katz, E. F., Provost, S. E., Selzer, J., Somoza, E. C., … Ling, W. (2011). Adjunctive counseling during brief and extended buprenorphine-naloxone treatment for prescription opioid dependence. Archives of General Psychiatry, 68(12), 1238-1246.
- Wen, R. Y., Atayee, R. S., & Edmonds, K. P. (2022). A comparison of institutional opioid equianalgesia tools: A national study. Journal of Palliative Medicine, 25(11), 1686-1691.
- World Health Organization. (2018). WHO guidelines for the pharmacological and radiotherapeutic management of cancer pain in adults and adolescents (Annex 6, Table A6.2). https://www.ncbi.nlm.nih.gov/books/NBK537482/