
Relapse means returning to substance use after a period of abstinence. It is not a failure but a common part of the recovery process, occurring in 40-60% of people with substance use disorders. Relapse develops through three predictable stages, emotional, mental and physical, and it can be prevented through evidence-based strategies including trigger identification, coping skills development, and ongoing support.
Understanding relapse as a process rather than an event allows for early intervention before substance use occurs.
Key Takeaways
- The National Institute on Drug Abuse puts relapse rates for substance use disorders at 40% to 60%. NIDA reports 50% to 70% for both hypertension and asthma, and attaches no fixed time window to either range.
- Relapse is a process, not an event; it unfolds in three stages (emotional, mental, physical) over days, weeks, or months before actual substance use occurs.
- The first 90 days of recovery carry the highest relapse risk, per Rajita Sinha’s 2011 review in Current Psychiatry Reports, and risk falls as abstinence lengthens. No single figure describes the 90-day rate across substances and treatment settings, so the useful measure is the trajectory rather than a headline percentage.
- Stress is the most commonly reported relapse trigger, followed by exposure to substance-related cues and negative emotional states.
- Mindfulness-based relapse prevention is used alongside cognitive-behavioural approaches to reduce relapse risk.
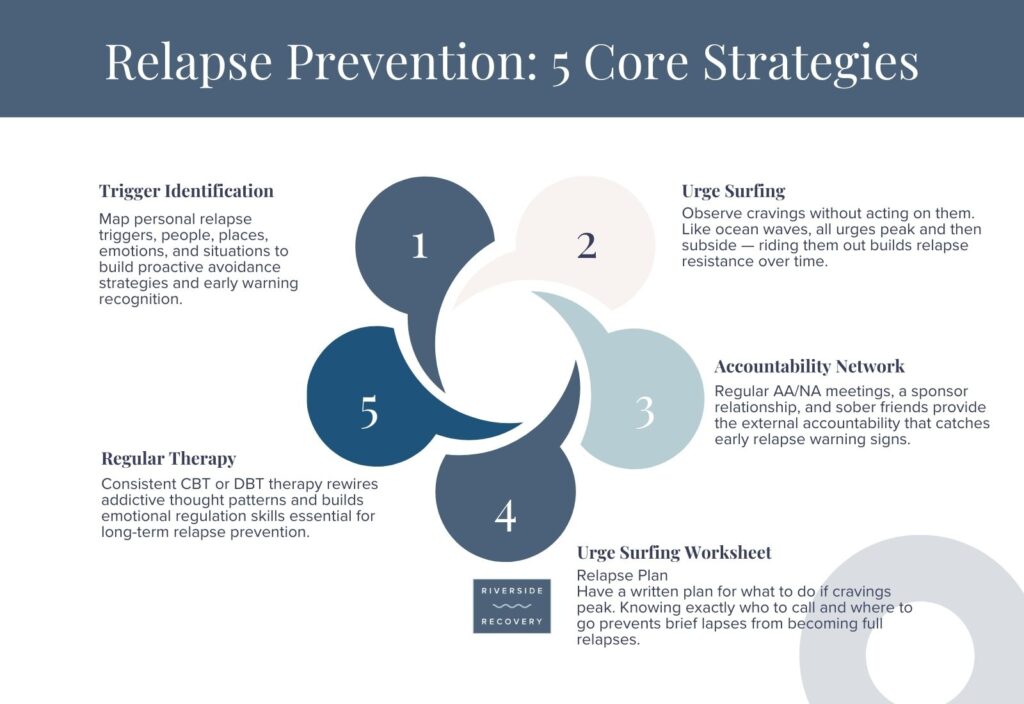
- A written relapse prevention plan gives a person specific, rehearsed responses to their own high-risk situations rather than improvised ones.
- People with strong social support relapse less often than those without supportive relationships.
- Medication-assisted treatment combined with behavioural therapy and counselling improves retention and reduces return to opioid use compared with either approach alone.
What Does Relapse Mean?
Relapse is a return to substance use after a period of abstinence, ranging from a single lapse to a sustained return to earlier patterns. NIDA records relapse in 40% to 60% of people treated for a substance use disorder, a recurrence of symptoms rather than a failure of character.
Relapse in addiction is not:
- A moral failure or character weakness
- Evidence that treatment doesn’t work
- A reason to give up on recovery
- An inevitable outcome
Relapse is:
- A common part of chronic disease management
- An opportunity to learn and strengthen recovery
- A signal that treatment needs adjustment
- A process that can be interrupted and prevented
Relapse occurs across a spectrum from brief lapses (single instances of use) to full returns to regular substance use patterns.
The clinical definition covers three dimensions:
- Duration: Any return to use, from one-time slip to sustained use
- Severity: Ranging from a brief lapse to a complete return to addiction
- Context: Occurring after a conscious decision to stop or reduce use
Addiction medicine distinguishes between lapse (a single instance of use) and relapse (return to regular use patterns). However, both require attention and intervention.
What Does a Relapse Signal About the Treatment Plan?
A relapse signals four gaps in the treatment plan: an unidentified trigger, a missing coping skill, a level of care that needs adjusting, and a vulnerability the plan can now address. Relapse marks the point where circumstances outran the person’s coping capacity, not a failure of intent.
Relapse signals:
- Unaddressed triggers: Environmental, emotional, or social factors that weren’t recognized or managed effectively
- Insufficient coping skills: Gap between the challenges faced and the tools available to handle them
- Need for treatment adjustment: Current recovery approach may need modification or intensification
- Opportunity for growth: Chance to identify vulnerabilities and strengthen recovery foundation
Understanding what relapse means helps remove stigma while maintaining accountability. Recovery continues after relapse when the person re-engages with treatment and support.
Is Relapse a Part of Recovery?
Relapse is common in recovery but not required for it: NIDA reports relapse in 40% to 60% of people treated for a substance use disorder, so a substantial share never relapse. Clinicians treat relapse as a signal to adjust the care plan, not as failed treatment.
Relapse is considered part of recovery because:

- Addiction is a chronic disease: Like type 2 diabetes, hypertension, or asthma, substance use disorders involve periods of symptom management and occasional setbacks. McLellan, Lewis, O’Brien and Kleber argued in JAMA in 2000 that drug dependence should be insured, treated and evaluated like other chronic illnesses.
- Recovery is a learning process: Each challenge, including relapse, provides information about vulnerabilities, triggers, and needed skills. People who address the gaps a relapse exposes strengthen their recovery afterwards.
- The brain takes time to heal: Neuroplasticity, the brain’s ability to rewire itself, occurs gradually over months and years. During this healing period, old pathways remain vulnerable to reactivation.
- However, relapse is not required for successful recovery: A substantial share of people reach lasting sobriety without returning to use. Prevention strategies, strong support systems, and early intervention lower that risk further.
What Is Relapse Prevention?
Relapse prevention is the practice of identifying a person’s own risk factors and rehearsing specific responses before those situations arise. Relapse prevention targets the emotional and mental stages of relapse, which precede substance use by days or weeks, instead of reacting once physical relapse has begun.
What Are the Core Relapse Prevention Strategies?
Eight core strategies prevent relapse: identifying triggers, developing coping mechanisms, building a support network, maintaining treatment engagement, practising self-care, creating a structured routine, monitoring warning signs, and writing an emergency plan. Each strategy is set out below:
Identify Personal Triggers
Triggers are situations, emotions, people, or places that increase urges to use substances.
Common triggers include:
- Stress (work, relationships, finances)
- Negative emotions (anger, loneliness, anxiety, depression)
- Positive emotions (celebrations, success)
- Environmental cues (places where you used, people you used with)
- Physical discomfort (pain, illness, fatigue)
Create a comprehensive trigger list and develop specific coping plans for each.
Develop Healthy Coping Mechanisms
Replace substance use with positive coping strategies:
- Physical exercise, which is used in recovery to reduce craving intensity
- Mindfulness and meditation
- Creative expression (art, music, writing)
- Social connection
- Sleep hygiene
- Proper nutrition
Build a Strong Support Network
A stable support network lowers a person’s relapse risk. Effective support includes:
- 12-step programs (AA, NA) or alternative peer support
- Individual therapy
- Group counseling
- Sober friends and family
- Sponsor or accountability partner
Maintain Treatment Engagement
Ongoing participation in recovery activities strengthens sobriety, including:
- Regular therapy appointments
- Support group attendance
- Medication-assisted treatment (if appropriate)
- Continuing care programs
- Skill-building workshops
Practice Self-Care
Physical and mental health maintenance supports recovery by following the practices mentioned below:
- Consistent sleep schedule
- Balanced nutrition
- Regular exercise
- Stress management
- Medical care for co-occurring conditions
Create a Structured Routine
Structure reduces decision fatigue and exposure to risky situations. Follow a structured routine as follows:
- Consistent daily schedule
- Planned activities and commitments
- Healthy habits and rituals
- Purpose-driven goals
Monitor Warning Signs
Early detection of the following changes allows intervention before physical relapse:
- Emotional changes (increased irritability, mood swings)
- Behavioral changes (isolating, missing meetings)
- Cognitive changes (romanticizing past use, minimizing consequences)
- Physical changes (poor self-care, sleep disruption)
Have an Emergency Plan
Prepare for high-risk situations in advance as follows:
- List of people to call when urges arise
- Coping strategies ranked by effectiveness
- Safe places to go during cravings
- Reasons for staying sober (written reminders)
Relapse Prevention Plan Components
A written relapse prevention plan should include:
- Personal motivation for recovery: Why sobriety matters to you
- Trigger list: Specific situations, emotions, and people that increase risk
- Warning signs: Early indicators that recovery is weakening
- Coping strategies: Specific techniques for managing triggers and urges
- Support contacts: Names and phone numbers of people to call
- Treatment resources: Therapist, support groups, crisis lines
- Emergency response: Step-by-step actions to take when urges are strong
What Are the Three Stages of Relapse?
Relapse unfolds in three stages: emotional, mental and physical. Emotional relapse begins when self-care lapses before any thought of using. Mental relapse follows, when part of the person wants to use while part resists. Physical relapse is the return to use itself.
The first two stages run for days or weeks, the window where intervention still works. The following are the stages of relapse:
Stage 1: Emotional Relapse
During emotional relapse, you’re not thinking about using, but your emotions and behaviors are setting up future relapse. You’re not taking care of yourself properly.
Signs of emotional relapse:
- Bottling up emotions
- Isolating from the support system
- Missing meetings or therapy
- Poor sleep and eating habits
- Focusing on others’ problems instead of your own
- Increased irritability and mood swings
Return to self-care basics. Resume support meetings. Talk about feelings. Practice stress management.
Stage 2: Mental Relapse
During mental relapse, part of you wants to use while another part fights against it. This internal conflict creates significant stress.
Signs of mental relapse:
- Thinking about people, places, and things associated with past use
- Romanticizing past substance use
- Lying or minimizing recovery commitment
- Planning relapse scenarios (“just once won’t hurt”)
- Considering situations where you could use
- Fantasizing about using
Talk to someone immediately. Attend extra support meetings. Review the consequences of past use. Use distraction and urge management techniques.
Stage 3: Physical Relapse
Physical relapse is the actual return to substance use. Once this stage begins, the opportunity for prevention has passed. The focus shifts to stopping use as quickly as possible and preventing full relapse into regular use patterns.
Contact the support system immediately. Return to treatment. Don’t use a single slip as permission for continued use. Implement the emergency plan.
What Is the Relapse Prevention Model?
The Relapse Prevention Model, developed by Marlatt and Gordon in 1985, explains relapse through four elements. The model names the high-risk situation, the coping response to it, outcome expectancies about using, and the abstinence violation effect that turns one lapse into a full return to use.
Key Components of the Relapse Prevention Model
- High-Risk Situations: Circumstances that increase relapse vulnerability. These include negative emotional states, interpersonal conflicts, and social pressure.
- Coping Response: How a person responds to high-risk situations. Effective coping leads to increased self-efficacy. Ineffective coping increases relapse risk.
- Outcome Expectancies: Beliefs about the effects of substance use. Positive expectancies (“it will help me relax”) increase relapse likelihood.
- Abstinence Violation Effect (AVE): The psychological reaction after an initial lapse. Guilt and failure attribution turn a one-time slip into a full relapse. Viewing a lapse as a learning opportunity reduces this effect.
Relapse Prevention Strategies from the Model
- Cognitive Restructuring: Challenge thoughts that minimize consequences or romanticize past use
- Behavioral Skills Training: Develop refusal skills, assertiveness, and stress management
- Lifestyle Modification: Create a balanced life, reducing relapse vulnerability
- Relapse Rehearsal: Mentally practice handling high-risk situations
- Urge Management: Techniques for riding out cravings without acting on them
Why Does Relapse Prevention Matter?
Relapse prevention matters most because the return to use after abstinence is the single most dangerous moment in a substance use disorder. Tolerance falls during abstinence, so the previous dose becomes an overdose dose. The remaining costs are medical, psychological, relational and legal.
Physical health risks of relapse include:
- Overdose risk increases after a period of abstinence (tolerance decreases)
- Medical complications from returning to use
- Increased risk of infectious diseases
- Organ damage accumulation
Psychological costs of relapse include:
- Shame and guilt that impede recovery
- Decreased self-efficacy and confidence
- Worsening co-occurring mental health conditions
- Increased risk of suicide
Social and practical consequences of relapse include:
- Damaged relationships and lost trust
- Employment and financial problems
- Legal issues and incarceration risk
- Loss of housing or custody
Recovery impact includes:
- Time lost rebuilding progress
- Increased difficulty achieving sobriety
- Potential need for a higher level of care
- Risk of chronic relapsing pattern
Prevention is always more effective and less costly than managing relapse consequences.
What Are the Reasons Not to Relapse?
Five groups of reasons hold people back from relapse: health, relationships, personal identity, practical stability, and the future. Lost tolerance turns a previous dose into an overdose risk, trust rebuilds slowly, and each additional sober day compounds the value of the last.
Health reasons include:
- Your body has begun healing, but relapse reverses this progress
- The risk of overdose is highest after a period of abstinence
- Each relapse causes additional brain and organ damage
- Mental health improves with sustained sobriety
Relationship reasons include:
- People who love you are supporting your recovery
- Trust takes years to rebuild but moments to destroy
- Your children need you to be present and healthy
- Relationships deepen and improve in recovery
Personal reasons include:
- You’re becoming who you want to be
- Freedom from addiction’s control
- Self-respect and dignity
- The achievement of goals is impossible while using
Practical reasons include:
- Job and financial stability depend on sobriety
- Legal consequences of returning to use
- Housing security
- Custody of children
Future reasons include:
- Opportunities available in recovery close if you relapse
- Each day sober builds a foundation for a better life
- Recovery gets easier the longer you maintain it
- Your future self will thank you for staying strong today
Keep these reasons visible during challenging moments. People in recovery write these lists down and review them during urges.
What Should You Do When Someone Relapses?
A helpful response to someone’s relapse combines five actions: express concern without judgment, offer practical help, listen without lecturing, encourage an immediate return to care, and set protective boundaries. Your response shapes how quickly that person re-engages with treatment.
Dos:
- Express concern without judgment
- Offer specific help (rides to treatment, attending meetings together)
- Listen without lecturing
- Encourage immediate return to treatment
- Set appropriate boundaries for your own well-being
- Remind them recovery is still possible
Don’ts:
- Enable continued use by providing money or excuses
- Shame or berate them
- Give up on their recovery
- Take their relapse personally
- Prevent them from experiencing natural consequences
- Force solutions they’re not ready for
Specific actions:
- Help them contact their therapist or treatment center
- Offer to attend a support meeting with them
- Remove substances from the shared living space
- Research treatment options if needed
- Take care of your own emotional needs
- Join a support group for families (Al-Anon, Nar-Anon)
Remember: You cannot control another person’s recovery. You can offer support while maintaining healthy boundaries.
“A relapse is a clinical event, not a verdict on the person. What we look at is where in the sequence it started, because emotional relapse shows up in behaviour weeks before anyone picks up. At Riverside Recovery of Tampa the same therapist carries a client from detox through residential, which is what makes those early changes visible to someone who knows what the person looked like at intake. When somebody returns after a relapse we re-run the biopsychosocial assessment rather than resuming the old plan, because the plan is what needs to change.”
Jackie Fink, LMHC, CAP, Clinical Director, Riverside Recovery of Tampa
What Resources Support Relapse Prevention?
Relapse prevention resources fall into five groups: crisis lines, 12-step and SMART Recovery meetings, professional outpatient and residential treatment, medications for alcohol and opioid use disorder, and digital recovery tools. Crisis lines come first here because they answer at any hour.
Crisis Support:
- 988 Suicide and Crisis Lifeline: call or text 988, or chat at 988lifeline.org (24/7, free, confidential)
- SAMHSA National Helpline: 1-800-662-HELP (4357) (24/7, free, confidential, treatment referral)
- Crisis Text Line: text HOME to 741741
12-Step Programs:
- Alcoholics Anonymous (AA)
- Narcotics Anonymous (NA)
- SMART Recovery (alternative approach)
Professional Treatment:
- Outpatient counseling
- Intensive Outpatient Programs (IOP)
- Partial Hospitalization Programs (PHP)
- Residential treatment (if needed)
Medication-Assisted Treatment:
- Buprenorphine (Suboxone) for opioid use disorder
- Naltrexone (Vivitrol) for alcohol and opioid use disorder
- Acamprosate (Campral) for alcohol use disorder
- Disulfiram (Antabuse) for alcohol use disorder
Digital Resources:
- Sobriety apps (I Am Sober, Sober Time, Nomo)
- Online support communities
- Telehealth therapy
- Recovery podcasts and videos
Relapse Prevention FAQs
How long does it take to reduce relapse risk?
Relapse risk falls after the first 90 days and keeps falling through the first year, then continues to decline with sustained abstinence. No single published figure fixes the point at which risk matches the general population, so treat the direction as reliable and any specific year-count as an estimate.
Can you prevent relapse completely?
No plan guarantees against relapse, but comprehensive prevention strategies lower the risk. People do reach lifelong recovery without relapsing.
What if I relapse after years of sobriety?
Late relapses occur but are less common. Return to treatment immediately. Years of recovery created neural pathways and skills that remain available. Recovery can be re-established more quickly than initial treatment.
Is relapse worse after longer sobriety?
Physiologically, yes: tolerance drops during abstinence, which raises overdose risk. Psychologically, the impact varies. Certain people return to treatment faster because they value what recovery gave them. Others struggle with shame.
Do I need to restart my sober date after a lapse?
Sober-date counting is a personal choice. 12-step programs typically restart the count. What matters most is returning to abstinence and learning from the experience.
References
- National Institute on Drug Abuse (NIDA). (2020). Treatment and Recovery. nida.nih.gov
- McLellan, A.T., Lewis, D.C., O’Brien, C.P., & Kleber, H.D. (2000). Drug dependence, a chronic medical illness: implications for treatment, insurance, and outcomes evaluation. JAMA, 284(13), 1689–1695. PubMed 11015800
- Sinha, R. (2011). New findings on biological factors predicting addiction relapse vulnerability. Current Psychiatry Reports, 13(5), 398–405. PMC3674771
- Marlatt, G.A., & Gordon, J.R. (1985). Relapse Prevention: Maintenance Strategies in the Treatment of Addictive Behaviors. Guilford Press.