




Bupropion (Wellbutrin, Zyban) withdrawal produces a discontinuation syndrome that is real, clinically significant, and distinct from antidepressant discontinuation syndromes of SSRIs or SNRIs. It is because of bupropion’s unique mechanism as a norepinephrine-dopamine reuptake inhibitor (NDRI) without serotonergic activity.
Bupropion withdrawal symptoms range from mild flu-like discomfort and irritability to significant fatigue, low mood and irritability. Bupropion carries a dose-related seizure risk while it is being taken, and it is contraindicated in anyone who is abruptly discontinuing alcohol, benzodiazepines, barbiturates or antiepileptic drugs. Understanding what bupropion withdrawal involves, how long it lasts, and when to seek clinical management is essential for safe discontinuation of one of the most commonly prescribed antidepressants in the United States.
Key Takeaways
- Bupropion carries a dose-related seizure risk while it is being taken, approximately 0.1 percent at doses up to 300mg per day. The FDA label does not identify stopping bupropion as a seizure risk, but it does contraindicate bupropion in anyone abruptly discontinuing alcohol, benzodiazepines, barbiturates or antiepileptic drugs.
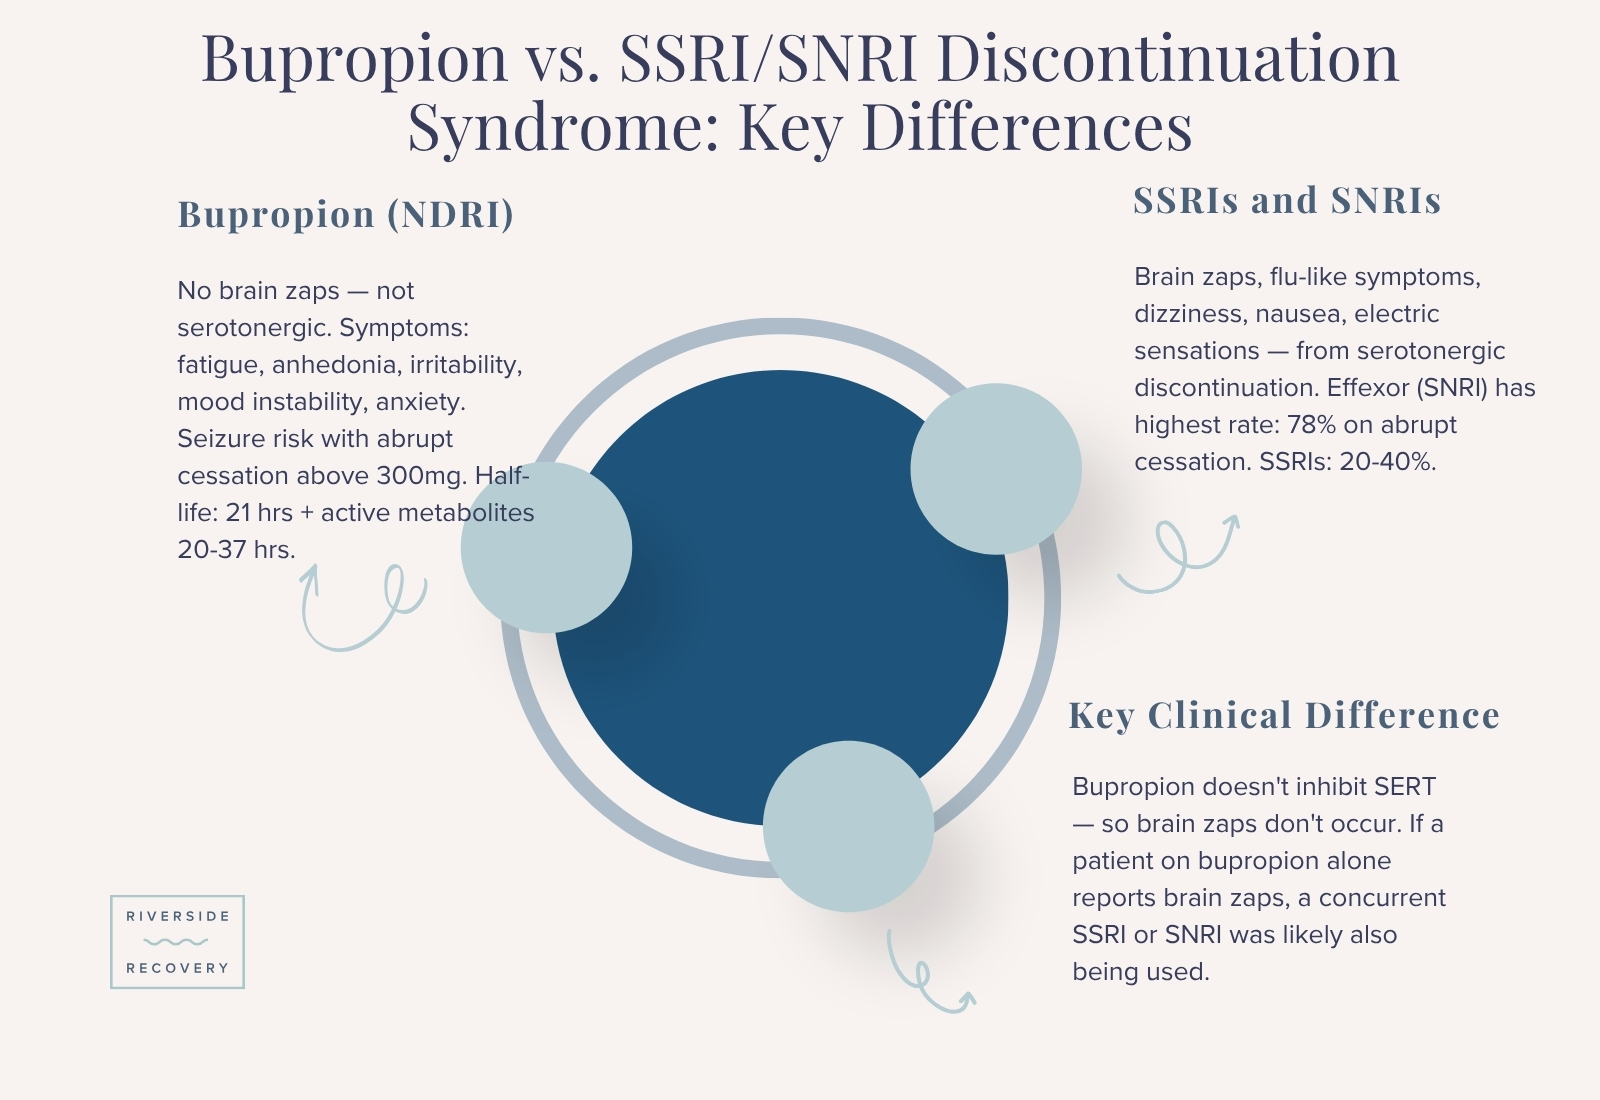
- Bupropion withdrawal does not produce the classic SSRI/SNRI discontinuation syndrome features (brain zaps, flu-like symptoms, electric sensations) because bupropion does not inhibit serotonin reuptake; instead it produces noradrenergic and dopaminergic withdrawal symptoms including fatigue, anhedonia, and increased craving in individuals with addiction histories.
- Bupropion is FDA-approved for major depressive disorder, seasonal affective disorder, and smoking cessation (Zyban); its dopaminergic mechanism makes it a preferred antidepressant option in some addiction medicine contexts due to lower abuse potential compared to stimulants.
- The withdrawal timeline for bupropion is typically shorter than SSRIs or SNRIs due to its 21-hour half-life, with most symptoms appearing within 48 to 72 hours of last dose and resolving within 2 weeks for most patients on therapeutic doses.
- A structured dose taper reduces withdrawal symptom severity and should be completed under prescriber supervision for any patient on more than 150mg per day for more than 6 weeks.
What Is Bupropion (Wellbutrin)?
Bupropion is an aminoketone antidepressant classified as a norepinephrine-dopamine reuptake inhibitor (NDRI), the only commonly prescribed antidepressant in its class. It was developed by Burroughs Wellcome (now GlaxoSmithKline) and first FDA-approved in 1985. It is available in immediate-release (IR), sustained-release (SR), and extended-release (XL) formulations under the brand names Wellbutrin, Wellbutrin SR, Wellbutrin XL, and Zyban.
How Bupropion Works
Bupropion inhibits the dopamine transporter (DAT) and norepinephrine transporter (NET), increasing synaptic dopamine and norepinephrine concentrations in the prefrontal cortex and mesolimbic circuits. It does not inhibit the serotonin transporter (SERT) and has no meaningful serotonergic activity at clinical doses.
- Primary mechanism: DAT and NET inhibition increasing prefrontal dopamine and norepinephrine availability
- Secondary mechanism: Nicotinic acetylcholine receptor antagonism, which contributes to its smoking cessation efficacy
- Half-life: 21 hours (bupropion); active metabolites hydroxybupropion (20 hours), threohydrobupropion (37 hours), and erythrohydrobupropion (33 hours) extend pharmacological activity
- Metabolism: CYP2B6 primary metabolism; CYP2B6 poor metabolizers achieve higher plasma concentrations with elevated seizure and side effect risk
- Available doses: IR: 75mg, 100mg; SR: 100mg, 150mg, 200mg; XL: 150mg, 300mg, 450mg
Bupropion and the Seizure Threshold
Bupropion has a dose-dependent seizure risk that distinguishes it from all other commonly prescribed antidepressants. At doses up to 300mg per day, the seizure incidence is approximately 0.1 percent, comparable to SSRIs. Above 450mg per day, seizure incidence rises to approximately 0.4 percent. Per the FDA label, this seizure risk is amplified by a history of bulimia or anorexia nervosa, seizure disorder, severe head injury, CNS tumor, and concurrent medications or substances that lower the seizure threshold including tramadol, alcohol, and stimulants.
Bupropion Withdrawal Symptoms
Because bupropion’s mechanism is noradrenergic and dopaminergic rather than serotonergic, its discontinuation syndrome differs from SSRIs and SNRIs. Brain zaps and electric sensations are not characteristic. Instead, bupropion withdrawal reflects norepinephrine and dopamine availability decline.
Common Withdrawal Symptoms
- Fatigue and energy crash: Loss of the noradrenergic and dopaminergic support for energy, motivation, and drive that bupropion provides produces marked fatigue and reduced initiation capacity during discontinuation
- Irritability and mood instability: Rapid mood changes, low frustration tolerance, and emotional volatility from norepinephrine withdrawal in the locus coeruleus and limbic circuits
- Anhedonia: Reduced capacity to experience pleasure from dopaminergic withdrawal reflects the removal of the DAT inhibition that maintained elevated synaptic dopamine; this is particularly pronounced in patients who began bupropion for depression with significant anhedonia
- Flu-like symptoms: Mild nausea, headache, and diaphoresis from autonomic destabilization as norepinephrine availability decreases
- Anxiety and agitation: Paradoxical anxiety from noradrenergic rebound and loss of dopaminergic prefrontal support for emotional regulation
- Sleep disruption: Insomnia or hypersomnia depending on individual noradrenergic and dopaminergic baseline; bupropion’s stimulating properties during treatment may have been managing insomnia symptoms that return during discontinuation
Severe Symptoms Requiring Medical Attention
- Seizures: Bupropion carries a dose-related seizure risk while it is being taken, and that risk is higher in patients with a history of bulimia or anorexia nervosa, prior seizures, or concurrent medications and substances that lower the seizure threshold. Anyone who is also abruptly discontinuing alcohol, benzodiazepines, barbiturates or antiepileptic drugs should be under medical supervision, because bupropion is contraindicated in that situation
- Severe anxiety or panic: Noradrenergic rebound can produce panic attacks and severe anxiety that are clinically indistinguishable from recurrence of the anxiety disorder that bupropion was treating
- Psychotic symptoms: Rare cases of psychotic symptoms during bupropion withdrawal have been reported, potentially reflecting dopaminergic dysregulation during the withdrawal period in predisposed individuals
Bupropion Wellbutrin Withdrawal Timeline
The withdrawal timeline for bupropion is shaped by both the parent compound’s 21-hour half-life and the longer half-lives of its active metabolites, which extend the pharmacologically active period beyond the parent compound alone.

- Hours 24 to 48 (Onset): Initial symptoms typically begin within 24 to 48 hours of last dose as bupropion parent compound clears; fatigue, irritability, and low mood are earliest signs
- Days 3 to 5 (Peak): As active metabolite levels decline, withdrawal symptoms reach maximum intensity, typically fatigue, irritability, anhedonia and mood instability
- Days 5 to 10 (Resolution for Most Patients): For patients on therapeutic doses who taper appropriately, most symptoms resolve within 7 to 10 days as the nervous system adapts to reduced DAT/NET inhibition
- Weeks 2 to 4 (Extended Course): Patients on high doses (450mg XL) or long-term therapy may experience lingering anhedonia and fatigue for 2 to 4 weeks as dopaminergic receptor sensitivity recalibrates
- Beyond 4 Weeks (Evaluate for Recurrence): Symptoms persisting beyond 4 weeks should be evaluated as potential recurrence of the underlying depressive or anxiety disorder rather than continued withdrawal
How to Safely Stop Bupropion
A structured dose taper is recommended for any patient on more than 150mg per day for more than 6 weeks, and is advisable at higher doses because withdrawal symptoms are more pronounced after a larger drop.
Taper Protocol
- Standard reduction rate: Reduce by 75 to 150mg per week over 2 to 4 weeks, adjusting speed based on symptom tolerance and dose level
- Step-down from XL to SR formulation: Converting from Wellbutrin XL to SR or IR before tapering provides more flexible dose increments for a smoother reduction schedule
- Never abrupt cessation above 300mg: Tapering rather than stopping abruptly reduces the severity of withdrawal symptoms such as fatigue, irritability and low mood. The FDA label gives no tapering schedule for bupropion, so pacing is a clinical judgment for the prescriber
- Prescriber involvement required: Any patient wishing to stop bupropion should inform their prescribing physician; self-discontinuation without tapering guidance is the primary cause of preventable withdrawal complications
Bupropion Withdrawal in Addiction Recovery
Bupropion is uniquely relevant in addiction medicine because it is one of the few FDA-approved antidepressants that augments dopaminergic neurotransmission without the misuse potential of stimulants, making it a preferred option for treating depression in patients with stimulant or opioid use disorder where dopaminergic signaling is compromised. When bupropion is discontinued during addiction treatment, the withdrawal’s anhedonia and energy crash can increase relapse risk during the already vulnerable early recovery period.
Treatment at Riverside Recovery of Tampa
Bupropion discontinuation that occurs during active addiction treatment requires careful clinical management to ensure that withdrawal symptoms are not confused with relapse triggers, and that any co-occurring psychiatric medication changes are supervised. At Riverside Recovery’s dual diagnosis program, psychiatric medication management is integrated into the treatment plan from admission.

Residential treatment provides continuous medical oversight during any psychiatric medication adjustments, including bupropion dose changes. Evidence-based therapy addresses the underlying depression and motivational deficits that bupropion treatment supports. All programs including IOP available with same-day assessment at (800) 871-5440.
Frequently Asked Questions
Does bupropion cause withdrawal?
Yes. Bupropion produces a discontinuation syndrome driven by noradrenergic and dopaminergic withdrawal rather than the serotonergic mechanisms of SSRI and SNRI withdrawal. Symptoms include fatigue, irritability, anhedonia, mood instability, and flu-like discomfort. Bupropion’s own seizure risk is dose-related while the drug is being taken, and the FDA label does not list stopping bupropion as a seizure risk.
What does bupropion withdrawal feel like?
Bupropion withdrawal typically feels like sudden loss of energy, motivation, and mood stability without the brain zaps or electric shock sensations characteristic of SSRI/SNRI withdrawal. Most patients describe fatigue, irritability, low mood, and a flat or empty emotional quality. Anxiety and agitation are common. Unlike serotonergic discontinuation syndromes, dizziness and sensory disturbances are uncommon.
How long does Wellbutrin withdrawal last?
With a structured taper from therapeutic doses, most bupropion withdrawal symptoms resolve within 7 to 14 days. Patients on high doses (300mg to 450mg) may experience lingering anhedonia and fatigue for 2 to 4 weeks. Symptoms persisting beyond 4 weeks should be evaluated as potential underlying depression recurrence rather than continued withdrawal.
Is bupropion withdrawal dangerous?
For most patients on therapeutic doses following a supervised taper, bupropion withdrawal is uncomfortable but not medically dangerous. The seizure risk associated with bupropion is dose-related while the drug is being taken rather than a consequence of stopping it, and it is higher in patients with a history of bulimia or anorexia nervosa, prior seizures, or concurrent medications that lower the seizure threshold including tramadol, alcohol, and stimulants.
Can you stop bupropion cold turkey?
Abrupt discontinuation of bupropion at doses above 150mg is not recommended because withdrawal symptoms are more pronounced after a larger drop. A gradual taper reducing dose by 75 to 150mg per week over 2 to 4 weeks reduces symptom severity. Always consult your prescribing physician before stopping bupropion.
Does bupropion withdrawal cause brain zaps?
No. Brain zaps are a characteristic symptom of serotonergic antidepressant withdrawal (particularly SSRIs and SNRIs) that reflect aberrant serotonergic neural transmission. Bupropion does not inhibit serotonin reuptake, so brain zaps are not a typical bupropion withdrawal feature. If a patient experiences brain zaps during bupropion discontinuation, it may indicate a concurrent SSRI or SNRI was also being used.
References
- Settle, E. C. (1998). Bupropion sustained release: Side effect profile. Journal of Clinical Psychiatry, 59(Suppl. 4), 32–36.
- Stahl, S. M., Pradko, J. F., Haight, B. R., Modell, J. G., Rockett, C. B., & Learned-Coughlin, S. (2004). A review of the neuropharmacology of bupropion, a dual norepinephrine and dopamine reuptake inhibitor. Primary Care Companion to the Journal of Clinical Psychiatry, 6(4), 159–166.
- Warner, C. H., Bobo, W., Warner, C., Reid, S., & Rachal, J. (2006). Antidepressant discontinuation syndrome. American Family Physician, 74(3), 449–456.
- U.S. Food and Drug Administration. (2023). Wellbutrin XL (bupropion hydrochloride extended-release tablets): Prescribing information. FDA.
- Horowitz, M. A., & Taylor, D. (2019). Tapering of SSRI treatment to mitigate withdrawal symptoms. Lancet Psychiatry, 6(6), 538–546.
- American Psychiatric Association. (2022). Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR). American Psychiatric Publishing.
- Substance Abuse and Mental Health Services Administration. (2023). National Survey on Drug Use and Health, 2022 results. U.S. Department of Health and Human Services.