
Alcohol withdrawal headaches begin within 6 to 24 hours after the last drink and peak between 24 and 72 hours as the brain’s neurochemistry recalibrates to the absence of alcohol.
Most people experience significant relief within 4 to 7 days, though headaches persist beyond 8 days in people with severe alcohol use disorder. Knowing what drives these headaches, how long each phase lasts, and when symptoms require emergency care makes the withdrawal process safer and more manageable.
Key Takeaways
- Alcohol withdrawal headaches are a direct symptom of Alcohol Withdrawal Syndrome (AWS), caused by GABA-glutamate imbalance and trigeminal nerve activation as the brain readjusts to the absence of ethanol.
- Alcohol withdrawal symptoms manifest in approximately 50% of individuals who misuse alcohol, and symptoms peak in one to three days and can extend for up to two weeks.
- Headaches that worsen after 72 hours, or occur alongside seizures, hallucinations, or fever, require immediate emergency evaluation for delirium tremens.
- Withdrawal headaches are not always short-lived: alcohol withdrawal symptoms can extend for up to two weeks, and headache is one of the ten parameters measured on the CIWA-Ar scale.
- Medical detox guided by CIWA-Ar scoring reduces both headache severity and the risk of life-threatening complications including seizures and delirium tremens.
What Is an Alcohol Withdrawal Headache?
A headache from alcohol withdrawal is a neurologically driven pain response. The headache occurs when someone who drinks heavily on a regular basis abruptly reduces or stops alcohol intake, which triggers a hyperexcitable brain state that sensitizes pain-signaling pathways.
How Withdrawal Headaches Differ from Hangover Headaches
Withdrawal headaches and hangover headaches share surface-level similarities but arise from fundamentally different mechanisms at different points in time. There are 3 differences between withdrawal and hangover headaches:
- Hangover headaches: Appear within hours of heavy drinking, resolve within 24 hours, and result from acute dehydration, acetaldehyde accumulation, and vasodilation rather than neurochemical rebalancing
- Withdrawal headaches: Begin 6 to 24 hours after the last drink in people with physical alcohol dependence, persist for days rather than hours, and result from GABA receptor downregulation and glutamate pathway hyperactivation
- Key clinical distinction: A hangover headache does not signal dependence; a withdrawal headache does, and requires clinical assessment to determine whether medical detoxification is needed
Alcohol Withdrawal Migraine vs. Withdrawal Headache: Key Differences
Alcohol withdrawal activates the trigeminal pain pathway, producing headaches that share features with migraines but follow a predictable withdrawal timeline rather than individual migraine trigger patterns. There are 4 distinguishing features:
- Location: Withdrawal headaches present as diffuse, bilateral pressure; migraines are usually unilateral with throbbing quality
- Trigger: Withdrawal headaches are triggered by ethanol absence and GABA-glutamate imbalance; migraines are triggered by individual factors such as hormonal changes, sleep disruption, or specific foods
- Duration pattern: Withdrawal headaches follow the AWS timeline and resolve as the brain recalibrates; migraines resolve within 4 to 72 hours regardless of withdrawal status
- Co-occurrence risk: Individuals with pre-existing migraine disorder are at higher risk for severe withdrawal headaches because trigeminal sensitization from both conditions compounds pain signal intensity
What Causes Alcohol Withdrawal Headaches?
Alcohol withdrawal headaches arise from three simultaneous neurobiological processes that the brain initiates when ethanol is abruptly removed after a period of chronic heavy exposure.

GABA-Glutamate Imbalance
Chronic ethanol exposure downregulates GABA-A receptor sensitivity and upregulates NMDA glutamate receptors as the brain compensates for alcohol’s depressant effects. When alcohol is removed, GABA inhibition drops sharply while glutamate excitatory activity surges unchecked, producing the neural hyperexcitability that generates headache alongside anxiety, tremors, and hypertension. There are 3 mechanisms:
- GABA pathway disruption: Chronic ethanol potentiates GABA-A receptors; withdrawal removes this potentiation, producing a sudden deficit in inhibitory tone throughout the central nervous system
- Glutamate surge: NMDA receptor upregulation during chronic drinking creates a rebound excitatory state when ethanol is removed, driving cortical spreading depolarization that activates pain-sensitive dural structures
- Norepinephrine release: Withdrawal activates the locus coeruleus, releasing norepinephrine that elevates blood pressure and amplifies pain signaling in the trigeminal system
Trigeminal Activation and Dura Mater Mast Cells
A 2024 study published in Neuron by Son and colleagues at the University of Texas Health Science Center identified MrgprB2 receptors on dura mater mast cells as a driver of alcohol-withdrawal headache in male mice. Mice lacking the receptor did not develop withdrawal headache behaviors at all. That result points to mast cell activation as the mechanism behind headaches more intense than standard tension-type presentations in people. There are 3 findings from the mouse model:
- MrgprB2 receptor activation: In the mouse model, alcohol withdrawal triggers MrgprB2-expressing mast cells in the dura mater to release neuropeptides, directly sensitizing trigeminal ganglia neurons and producing craniofacial pain hypersensitivity
- Trigeminal sensitization: Sensitized trigeminal ganglia neurons lower the threshold for pain signaling from the scalp, face, and neck, explaining why withdrawal headaches feel pressure-like and are worsened by light, movement, and noise
- Clinical implication: This neuroinflammatory pathway is distinct from the GABA-glutamate mechanism, meaning withdrawal headaches involve two simultaneous pain-generating processes that compound severity
Blood Pressure and Vascular Changes
Alcohol withdrawal produces a sympathetic nervous system surge that elevates blood pressure and constricts and dilates cerebral blood vessels, both of which directly generate headache. There are 3 vascular mechanisms:
- Hypertensive headache mechanism: Withdrawal-driven norepinephrine release elevates systolic blood pressure, producing hypertensive headache that adds a vascular component on top of the neuroinflammatory component
- Vasodilation rebound: As the acute withdrawal phase resolves, cerebral blood vessels that were constricted during active drinking undergo compensatory vasodilation, which activates pain-sensitive perivascular nerve endings
- Dehydration contribution: Chronic heavy drinking produces osmotic diuresis; the dehydrated state that accompanies withdrawal reduces plasma volume, further reducing cerebral perfusion pressure and intensifying headache
How Long Do Alcohol Withdrawal Headaches Last?
The duration of alcohol withdrawal headaches follows the AWS timeline, with headache intensity mirroring the overall trajectory of withdrawal severity from onset through resolution.

Stage-by-Stage Withdrawal Headache Timeline
Headaches after quitting alcohol follow the AWS symptom progression documented in clinical research, with headache tracked as one of the 10 measured parameters on the CIWA-Ar assessment tool.
- Hours 6 to 24 (Onset): Mild to moderate headache begins alongside anxiety, insomnia, and nausea. GABA-glutamate imbalance initiates neural hyperexcitability. Most individuals feel a dull, diffuse head pressure during this window.
- Hours 24 to 72 (Peak): Headache reaches maximum intensity as AWS symptoms peak. Blood pressure elevation, glutamate surge, and trigeminal sensitization converge. Hours 24 to 72 are the highest-risk window for seizures and delirium tremens.
- Hours 72 to 96 (Resolution Phase): For most people with mild to moderate AWS, headache begins to subside as GABA-glutamate balance begins to restore. Blood pressure stabilizes and neuroinflammatory signaling decreases.
- Days 4 to 7 (Continued Recovery): Most individuals experience significant headache reduction. Residual headache at this stage is driven by sleep disruption, nutritional depletion, and lingering sympathetic nervous system activation rather than acute withdrawal chemistry.
- Beyond Day 7 (Post-Acute Phase): In individuals with severe or long-standing alcohol use disorder, headaches persist as part of post-acute withdrawal syndrome (PAWS), which involves protracted neuroadaptation lasting weeks to months.
Factors That Determine How Long Headaches Last
5 clinical variables extend or shorten withdrawal headache duration beyond the standard 4 to 7-day window.
- Duration of heavy drinking: Years of daily heavy drinking produce deeper GABA receptor downregulation, requiring longer recalibration time and extending headache duration
- Daily alcohol volume: Higher daily ethanol consumption correlates with more severe GABA-glutamate disruption and a longer, more intense withdrawal headache trajectory
- Prior withdrawal episodes: Kindling effect from repeated withdrawal episodes progressively sensitizes the CNS, causing each subsequent withdrawal to produce more severe and longer-lasting headaches
- Pre-existing migraine history: Individuals with migraine disorder experience amplified trigeminal sensitization during withdrawal, extending headache duration and intensity
- Medical supervision: CIWA-Ar-guided benzodiazepine therapy directly reduces headache duration by suppressing the glutamate excitatory surge and lowering blood pressure within the first 24 to 48 hours
What Are the Symptoms of an Alcohol Withdrawal Headache?
Alcohol withdrawal produces a predictable spectrum of headache presentations from mild pressure to severe pain requiring immediate emergency evaluation, with headache intensity tracked as one of the 10 measured parameters on the CIWA-Ar scale.
Common Symptoms
The early symptoms appear in the majority of individuals undergoing alcohol withdrawal and emerge within the first 24 hours.
- Diffuse head pressure: A bilateral, non-pulsating pressure sensation affecting the forehead, temples, and base of the skull, driven by sympathetic nervous system activation and trigeminal sensitization
- Light and sound sensitivity: Lowered pain threshold in trigeminal ganglia neurons produces photophobia and phonophobia similar to migraine, making normal environments feel overstimulating
- Neck and shoulder tension: Withdrawal-driven muscle hypertonicity produces myofascial pain that radiates from the cervical spine to the base of the skull
- Worsening with movement: Head movement amplifies trigeminal pain signaling during the hyperexcitable withdrawal state, making walking or changing position uncomfortable
Severe Symptoms
The escalating symptoms indicate moderate to severe AWS and require clinical evaluation to determine whether medically supervised detox is necessary. There are 3 escalating symptoms:
- Throbbing, pulsating headache: Vascular headache component driven by blood pressure spikes above 140/90 mmHg, indicating that withdrawal is producing hemodynamic instability requiring monitoring
- Headache combined with confusion: Cognitive disorientation alongside severe headache reflects early delirium tremens or hypertensive encephalopathy, both requiring immediate assessment
- Headache exceeding 72 hours without improvement: Headache that does not begin to resolve after 72 hours suggests a complicated withdrawal course and warrants clinical reassessment and possible inpatient detox
Emergency Warning Signs
The emergency signs alongside headache constitute a medical emergency and require calling 911 or going to an emergency department immediately.
- Sudden severe headache described as “the worst of my life” indicates hypertensive crisis or intracranial hemorrhage requiring neurological evaluation
- Headache with fever above 38.5°C (101.3°F) alongside confusion, agitation, and hallucinations constitutes delirium tremens, which carries a substantial mortality risk without treatment and a low one with prompt medical management
- Headache immediately preceding a seizure indicates severe AWS requiring IV benzodiazepines, phenobarbital, or ketamine administered in an emergency setting
- Headache with visual disturbances or loss of consciousness requires immediate neurological assessment to rule out intracranial pathology secondary to hypertensive crisis
How Do You Stop Alcohol Withdrawal Headaches (Detox Headache Relief)?
Knowing how to stop alcohol withdrawal headaches means matching the intervention to the severity level, because strategies appropriate for mild headaches in early withdrawal are insufficient for moderate to severe AWS.
Home Management for Mild Withdrawal Headaches
The strategies above reduce headache severity in individuals with mild AWS (CIWA-Ar score below 9) who do not have a history of prior severe withdrawal, seizures, or delirium tremens.
- Oral hydration with electrolytes: Dehydration amplifies withdrawal headache intensity; replacing sodium, potassium, and magnesium through electrolyte-containing beverages or oral rehydration salts reduces the vascular component of headache
- Thiamine (vitamin B1) supplementation: Chronic heavy drinking depletes thiamine, which the brain requires for glucose metabolism. Oral thiamine alone does not reliably prevent Wernicke’s encephalopathy, because absorption is unreliable in alcohol use disorder and guideline prophylaxis for anyone at real risk is parenteral thiamine dosed by a clinician. Ask a clinician about thiamine rather than relying on an over-the-counter tablet
- Low-stimulation environment: Dimming lights, reducing noise, and minimizing screen time reduces trigeminal nerve stimulation and lowers the pain amplification that occurs during the hyperexcitable withdrawal state
- Acetaminophen (not NSAIDs): Acetaminophen at standard dosing (not exceeding 2g per day in those with alcohol-related liver involvement) provides mild headache relief; NSAIDs carry gastrointestinal bleeding risk in the context of heavy alcohol use, so use them cautiously
Clinical Treatment: CIWA-Ar Guided Medical Detox
The Clinical Institute Withdrawal Assessment for Alcohol, Revised (CIWA-Ar) is a validated 10-item clinical scale that quantifies AWS severity across headache, nausea, tremor, anxiety, hallucinations and orientation. CIWA-Ar scores range from 0 to 67, and they guide treatment escalation from observation through ICU-level care.
- Mild AWS (CIWA-Ar 0 to 8): Monitored observation, oral thiamine, hydration, and non-opioid analgesics for headache; benzodiazepines held unless symptoms escalate
- Moderate AWS (CIWA-Ar 9 to 15): Oral or IV benzodiazepines including lorazepam, diazepam, or chlordiazepoxide administered on a symptom-triggered protocol; parenteral thiamine administered before any glucose, the sequence that prevents Wernicke’s encephalopathy
- Severe AWS (CIWA-Ar 16 and above): IV benzodiazepines with phenobarbital or ketamine adjunct, seizure precautions, continuous hemodynamic monitoring, and ICU-level assessment for delirium tremens
- Headache-specific medications: Beta-blockers such as metoprolol or atenolol reduce headache intensity by controlling blood pressure surges; IV magnesium sulfate reduces both headache and seizure risk simultaneously in inpatient detox settings
How Does Riverside Recovery of Tampa Treat Alcohol Withdrawal Headaches?
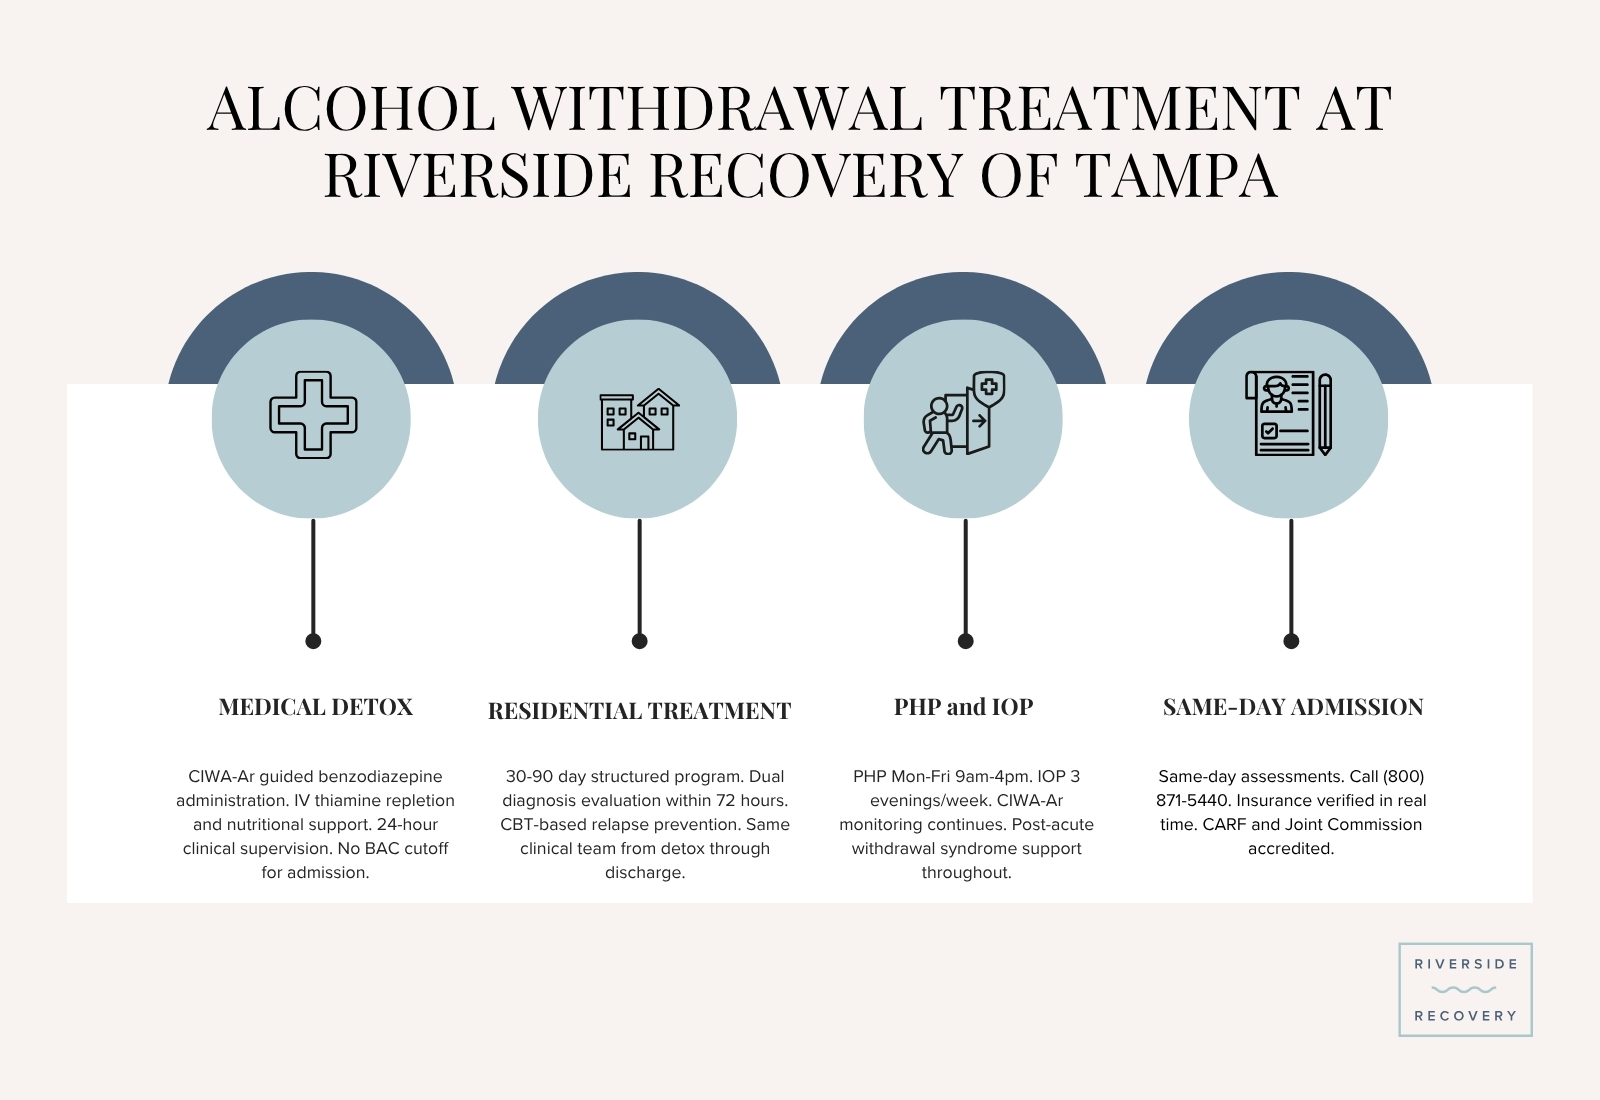
Medically supervised detoxification from alcohol at Riverside Recovery of Tampa uses CIWA-Ar-guided protocols to manage withdrawal headaches and the full spectrum of AWS safely, with the same clinical team providing continuity from detox through residential and outpatient levels of care.
Medical Detox
Riverside Recovery of Tampa’s medical detox unit monitors CIWA-Ar scores every 2 to 4 hours during the critical 6 to 72-hour onset-to-peak window. The unit administers benzodiazepines, IV thiamine and hemodynamic support based on real-time symptom trajectory rather than fixed-schedule protocols. There are 3 CIWA-Ar severity tiers:
- 24-hour clinical supervision: A five-provider medical team manages all medication titration, including beta-blocker administration for hypertensive headache and IV magnesium sulfate for moderate to severe presentations
- No BAC cutoff for admission: Patients presenting with active alcohol intoxication are admitted without requiring sobriety before intake, allowing immediate clinical stabilization
- PAWS monitoring: For patients whose headaches persist beyond 7 days, the clinical team evaluates for post-acute withdrawal syndrome and adjusts the care plan to address protracted neuroadaptation
Assistant Medical Director Erin Ikenberry, PA-C, whose emergency medicine background informs the facility’s AWS protocols, notes: “Withdrawal headaches are often the earliest clinical signal that someone is in a more serious withdrawal trajectory than they realize. We use CIWA-Ar scores in combination with blood pressure trends to determine when a headache needs medication management versus when it signals an escalating withdrawal course requiring more aggressive intervention.”
Residential Treatment
Residential treatment at Riverside Recovery of Tampa continues the care initiated during detox, with the same clinical team maintaining continuity throughout the 30 to 90-day program on the Hillsborough River campus.
- Dual diagnosis evaluation: Conducted within 72 hours of residential admission, this identifies co-occurring conditions such as anxiety disorder or migraine disorder that amplify withdrawal headache severity and require concurrent treatment
- Nutritional rehabilitation: Structured nutrition protocols address thiamine, magnesium, and B-vitamin depletion, which drives prolonged withdrawal headaches when left untreated beyond the acute detox phase
- CBT and DBT programming: Daily group therapy and twice-weekly individual sessions address the anxiety and hyperarousal that sustain sympathetic nervous system activation and extend headache duration into the post-acute phase
Day/Night Treatment and Intensive Outpatient
Step-down care runs through Day/Night Treatment (PHP, Monday through Friday, 9am to 4pm) and Intensive Outpatient (IOP, three evenings per week). That step-down supports patients through the post-acute withdrawal period when residual headaches, cognitive fog, and mood dysregulation require structured clinical oversight without inpatient admission.
All outpatient programs include MAT continuation, random urine drug screening, relapse prevention, and access to dual diagnosis treatment for co-occurring conditions that prolong withdrawal symptoms. Same-day assessments are available at (800) 871-5440, with most major private insurance accepted and benefits verified in real time.
“In our experience, patients whose withdrawal headaches extend into the second week typically have longer drinking history, multiple prior withdrawal episodes, or underlying migraine comorbidity. CIWA-Ar scores alone don’t always capture this trajectory, which is why we track blood pressure and headache severity as a combined indicator of where someone is in their withdrawal course.”
Frequently Asked Questions
Does alcohol withdrawal cause headaches?
Yes. Alcohol withdrawal causes headaches by triggering GABA-glutamate imbalance and trigeminal nerve sensitization when the brain recalibrates after chronic ethanol exposure is removed. Headache is one of the 10 measured parameters on the CIWA-Ar scale and appears in the majority of people experiencing AWS.
How long do headaches last after quitting alcohol?
Most alcohol withdrawal headaches resolve within 4 to 7 days as GABA-glutamate balance restores. In people with severe or long-standing alcohol use disorder, headaches can persist beyond 8 days as part of post-acute withdrawal syndrome. Medical detox shortens the duration by suppressing the glutamate excitatory surge within the first 48 hours.
What does an alcohol withdrawal headache feel like?
Alcohol withdrawal headaches typically feel like bilateral diffuse pressure, with light and sound sensitivity driven by trigeminal sensitization. Withdrawal headaches are more intense and longer-lasting than hangover headaches, often accompanied by neck tension and worsened by movement. Severe cases develop a pulsating, throbbing quality when blood pressure spikes during peak withdrawal.
Can alcohol withdrawal cause headaches after only stopping for one day?
Yes. Withdrawal headaches can begin within 6 to 24 hours of the last drink in people who have been drinking heavily for weeks, months, or years. The 6 to 24-hour onset window is well-established in clinical AWS research, and headache is often among the earliest symptoms to appear alongside anxiety and nausea.
How to Stop Alcohol Withdrawal Headaches: What Actually Works?
For mild withdrawal, oral hydration with electrolytes and acetaminophen at standard dosing provide relief. For moderate to severe withdrawal, CIWA-Ar-guided benzodiazepines plus IV thiamine and beta-blockers for blood pressure management are the clinical standard. NSAIDs carry gastrointestinal bleeding risk in heavy drinkers and should be used cautiously without medical guidance.
Can alcohol withdrawal cause a migraine?
Alcohol withdrawal activates the same trigeminal pathway that drives migraines, and individuals with pre-existing migraine disorder are at significantly higher risk for severe withdrawal headaches. A withdrawal headache is not clinically identical to a migraine but shares mechanisms including trigeminal sensitization, photophobia, phonophobia, and vascular pain components.
Is a headache after stopping drinking serious?
A headache that appears within 24 hours of stopping drinking after prolonged heavy use warrants clinical assessment. Headaches accompanied by fever, confusion, hallucinations, or seizures constitute a medical emergency. A headache that worsens instead of improving after 72 hours, or that persists beyond a week, requires evaluation for complicated AWS or PAWS.
When should I go to the emergency room for an alcohol withdrawal headache?
Go to the emergency room immediately where the headache is sudden and severe, occurs with fever or confusion, precedes or follows a seizure, or arrives with visual disturbances or loss of consciousness. The signs above indicate delirium tremens or hypertensive crisis, both of which are life-threatening without immediate IV treatment.
References
- Sullivan, J. T., Sykora, K., Schneiderman, J., Naranjo, C. A., & Sellers, E. M. (1989). Assessment of alcohol withdrawal: The revised Clinical Institute Withdrawal Assessment for Alcohol scale (CIWA-Ar). British Journal of Addiction, 84(11), 1353–1357.
- Son, H., Zhang, Y., Shannonhouse, J., Ishida, H., Gomez, R., & Kim, Y. S. (2024). Mast-cell-specific receptor mediates alcohol-withdrawal-associated headache in male mice. Neuron, 112(1), 113–123.
- National Institute on Alcohol Abuse and Alcoholism. (2023). Alcohol use disorder: A comparison between DSM-IV and DSM-5. U.S. Department of Health and Human Services. Retrieved from niaaa.nih.gov
- Tiglao, S. M., Meisenheimer, E. S., & Olson, K. L. (2021). Alcohol withdrawal syndrome. American Family Physician, 104(3), 253–262.
- Newman, R. K., Stobart Gallagher, M. A., & Gomez, A. E. Alcohol withdrawal syndrome. StatPearls. Treasure Island (FL): StatPearls Publishing. Available from: https://www.ncbi.nlm.nih.gov/books/NBK441882/
- Vasan, S., & Kumar, A. Wernicke encephalopathy. StatPearls. Treasure Island (FL): StatPearls Publishing. Available from: https://www.ncbi.nlm.nih.gov/books/NBK470344/
- Jesse, S., Braünig, P., & Ludolph, A. C. (2017). Alcohol withdrawal syndrome: Mechanisms, manifestations, and management. Acta Neurologica Scandinavica, 135(1), 4–16.
- American Psychiatric Association. (2022). Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR). American Psychiatric Publishing.
- Sachdeva, A., Choudhary, M., & Chandra, M. (2015). Alcohol withdrawal syndrome: Benzodiazepines and beyond. Journal of Clinical and Diagnostic Research, 9(9), VE01–VE07.
- Foy, A., March, S., & Drinkwater, V. (1988). Use of an objective clinical scale in the assessment and management of alcohol withdrawal in a large general hospital. Alcoholism: Clinical and Experimental Research, 12(3), 360–364.