

Yes, alcohol affects your period by disrupting the hypothalamic-pituitary-gonadal (HPG) axis.
The hormonal signaling chain that controls the menstrual cycle, leading to changes in estrogen and progesterone levels, altered timing of ovulation, and in heavy drinkers, irregular or missed periods. The degree of disruption depends on how much you drink, how often, and at which point in your cycle the drinking occurs.
Understanding these mechanisms helps explain why alcohol changes periods differently across individuals and drinking patterns.
Key Takeaways
- Alcohol disrupts the menstrual cycle primarily by suppressing gonadotropin-releasing hormone (GnRH) secretion, which impairs the release of luteinizing hormone (LH) and follicle-stimulating hormone (FSH) needed to trigger ovulation.
- Each standard alcoholic drink raises total estradiol by approximately 5.26 percent and luteinizing hormone by 6.18 percent, according to a prospective cohort study of 259 healthy premenopausal women published in The American Journal of Clinical Nutrition. Binge drinking is associated with higher total estradiol than non-binge drinking in the same body of research.
- Moderate alcohol consumption produces no statistically significant disruption to menstrual cycle function in short-term research, but heavy and chronic drinking is consistently associated with anovulation, irregular cycles, and amenorrhea.
- In the 2024 National Survey on Drug Use and Health, 27.9 million people ages 12 and older, or 9.7% of that age group, had alcohol use disorder in the past year, with women representing an increasingly large proportion of new-onset AUD diagnoses.
- The liver’s role in estrogen metabolism means alcohol-related liver dysfunction compounds hormonal disruption beyond the HPG axis effects alone.
How Does Alcohol Change Your Menstrual Cycle?
Alcohol disrupts the menstrual cycle through a hormonal cascade that begins in the hypothalamus and runs through the pituitary gland, the ovaries and the liver. The effects vary by drinking volume and by menstrual phase.
The HPG Axis and Why It Is Alcohol-Sensitive
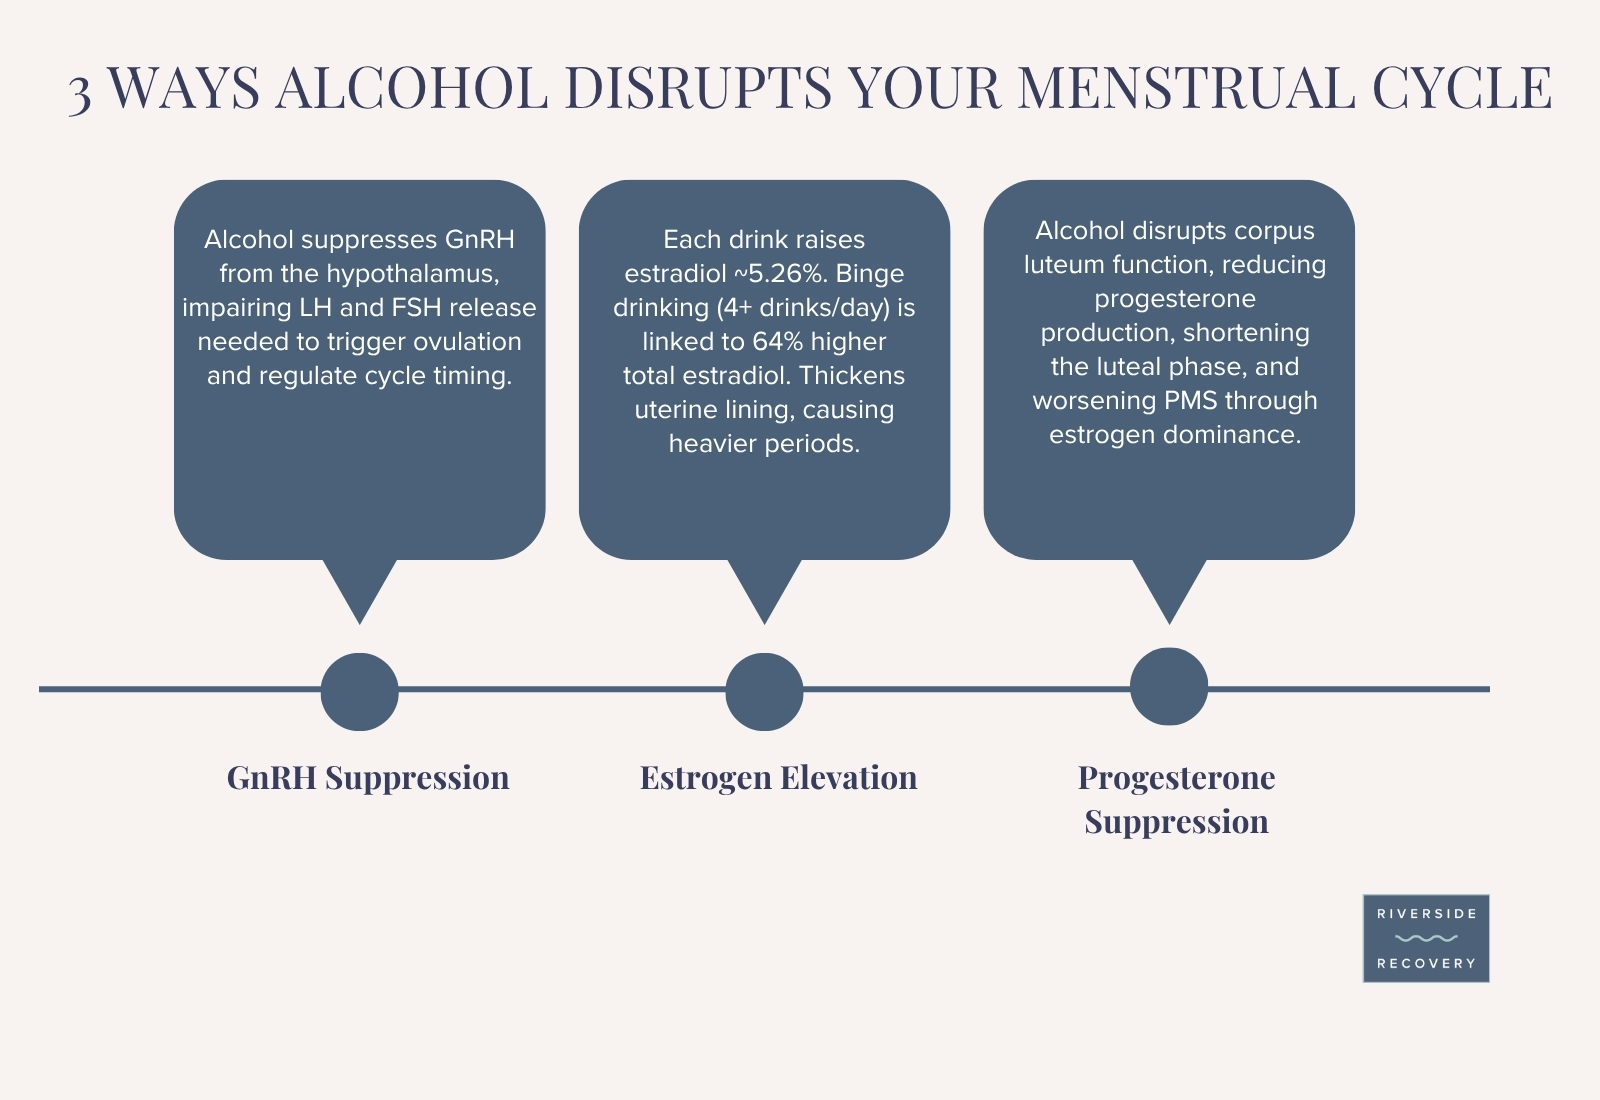
The hypothalamic-pituitary-gonadal (HPG) axis regulates the menstrual cycle through a precise hormonal cascade, and ethanol disrupts this cascade at 3 levels simultaneously.
There are 3 points where alcohol interrupts the HPG axis:
- Hypothalamic suppression: Ethanol reduces the pulsatile release of gonadotropin-releasing hormone (GnRH) from the hypothalamus, which is the master signal that initiates each cycle’s hormonal cascade
- Pituitary impairment: Reduced GnRH signaling impairs the pituitary gland’s release of luteinizing hormone (LH) and follicle-stimulating hormone (FSH), both of which are required for follicle development and ovulation
- Ovarian disruption: Diminished LH and FSH signals disrupt follicle maturation in the ovaries, which prevents the LH surge that triggers ovulation and altering the timing and length of the luteal phase
How Alcohol Elevates Estrogen
Alcohol raises estrogen levels through two mechanisms: direct stimulation of estrogen production in the ovaries and impairment of the liver’s ability to metabolize and clear circulating estrogen from the bloodstream.
There are 3 routes by which alcohol raises estrogen:
- Each drink raises estradiol by ~5%: A prospective cohort study found that each standard alcoholic drink was associated with a 5.26 percent increase in total estradiol and a 6.18 percent increase in LH after adjusting for confounding variables
- Binge drinking effect: Binge drinking (4 or more drinks per day) was associated with 64.35 percent higher total estradiol and 63.53 percent higher free estradiol compared to non-binge levels in the same study
- Liver metabolism impairment: Alcohol impairs hepatic estrogen clearance by competing for the liver enzymes that break down circulating estrogen, causing estrogen to accumulate beyond normal physiological levels
How Alcohol Lowers Progesterone
While alcohol raises estrogen, it simultaneously reduces progesterone levels through its disruption of the luteal phase, producing an estrogen-dominant hormonal environment that changes menstrual regularity, flow and symptoms.
There are 3 effects of lowered progesterone:
- Luteal phase shortening: Alcohol disrupts the LH surge that triggers corpus luteum formation after ovulation; a diminished or absent corpus luteum produces less progesterone, shortening the luteal phase and advancing the onset of the next period
- Steroid hormone binding globulin (SHBG): Alcohol reduces SHBG levels, which increases the proportion of free (biologically active) estrogen and testosterone in circulation relative to progesterone
- Progesterone-to-estradiol ratio: A 2024 study published in the American Journal of Psychiatry found that high progesterone-to-estradiol ratios had a protective effect against binge drinking, suggesting that the progesterone suppression driven by alcohol creates a bidirectional feedback loop that worsens alcohol use patterns in women with AUD
Does Alcohol Change Your Period Differently by Cycle Phase?
Alcohol’s effects on the menstrual cycle are phase-dependent. The disruption is sharpest in the follicular phase, where alcohol shifts LH surge timing, and in the late luteal phase, where progesterone is most vulnerable to suppression.
Follicular Phase Effects
The follicular phase runs from day 1, the first day of menstruation, through ovulation at around day 14. That window is where alcohol’s LH-suppressing effect carries the greatest weight over whether ovulation occurs at all.
There are 3 follicular phase effects of alcohol:
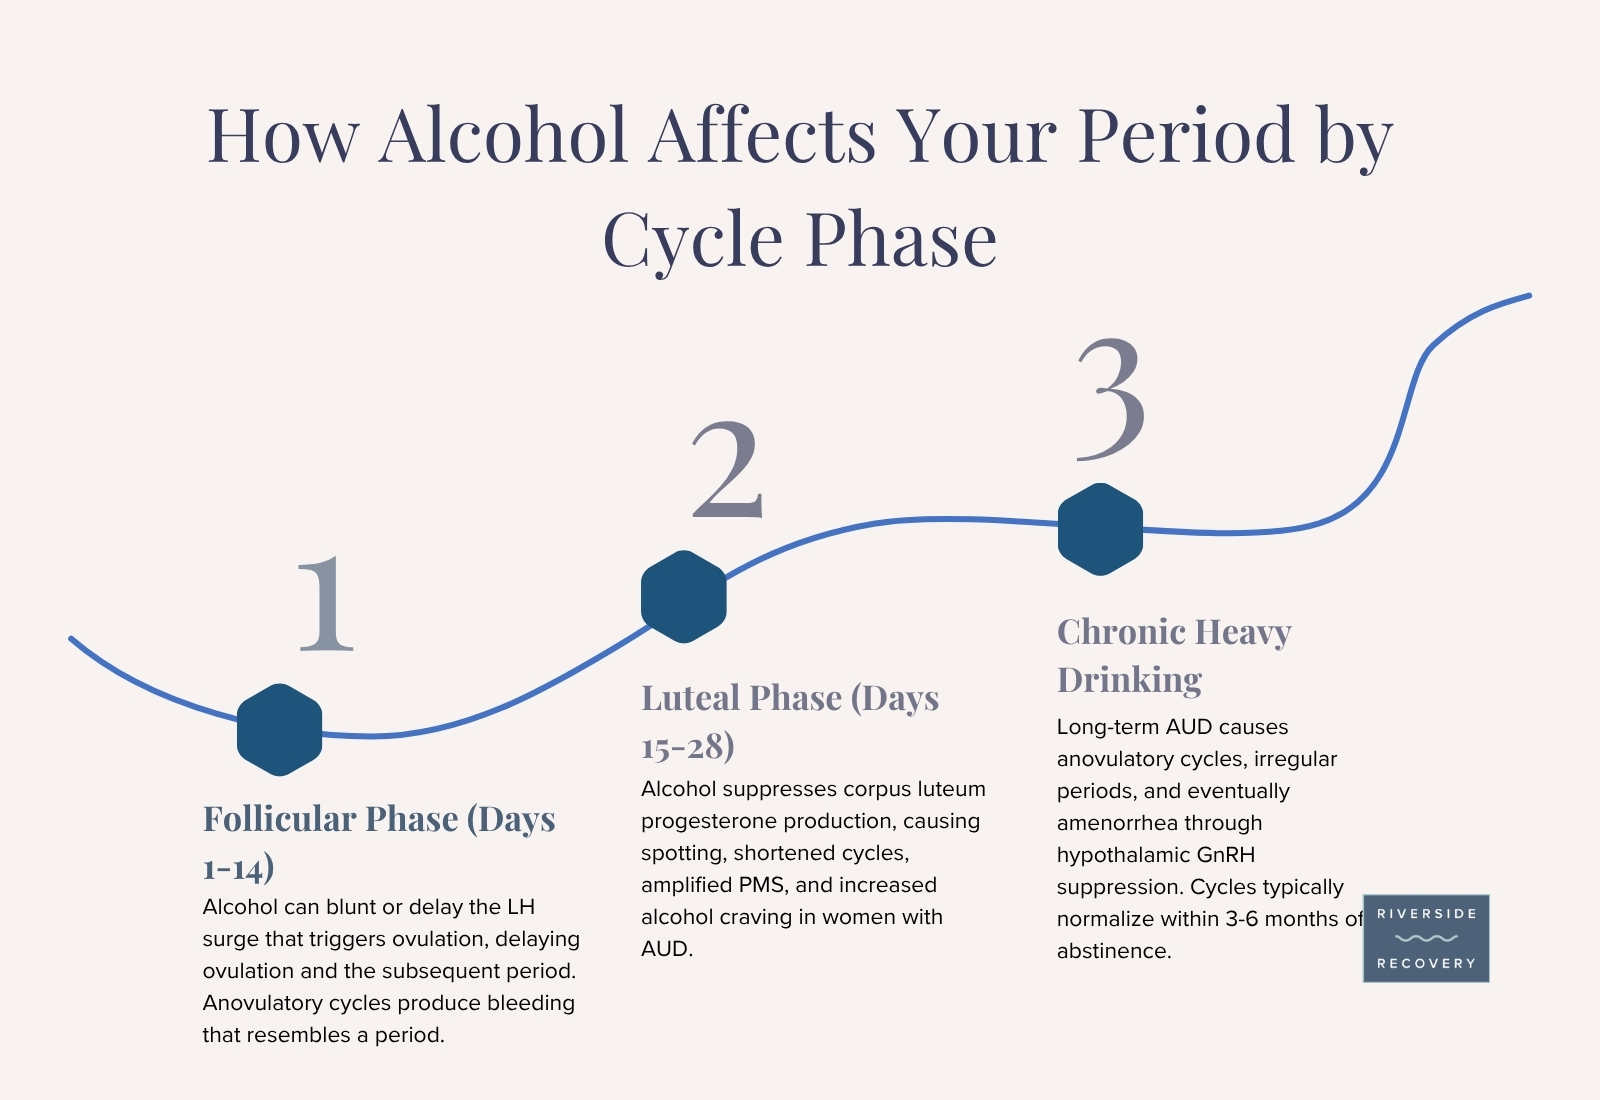
- Ovulation disruption: Alcohol consumed during the follicular phase blunts or delays the LH surge, which either prevents ovulation entirely (anovulatory cycle) or shifting ovulation to a later date, which delays the subsequent period
- Estradiol sensitivity: Research by Griffith et al. (2022) found that women showed heightened sensitivity to the disinhibiting effects of alcohol during the late follicular phase when estradiol is rising, suggesting that alcohol consumed during this window amplifies behavioral effects alongside its hormonal disruption
- Cycle length alteration: Delayed ovulation from alcohol-driven LH suppression extends the follicular phase and effectively lengthens the overall cycle, which the person experiences as a late period
Luteal Phase Effects
The luteal phase runs from ovulation through the end of the cycle, and the corpus luteum produces progesterone through it to prepare the uterine lining for potential implantation.
There are 3 luteal phase effects of alcohol:
- Progesterone suppression: Alcohol consumed during the luteal phase suppresses corpus luteum function and reduces progesterone production, which produces spotting, shortened cycles, or heavier than normal menstrual flow when progesterone drops prematurely
- PMS amplification: The estrogen-progesterone imbalance created by alcohol in the luteal phase amplifies premenstrual syndrome (PMS) symptoms including mood instability, bloating, cramping, and breast tenderness by prolonging the relative estrogen excess that characterizes the late luteal window
- Luteal phase alcohol cravings: Low progesterone during the late luteal phase tracks with increased alcohol craving and consumption in women with AUD, creating a cyclical vulnerability pattern documented in the 2024 Hoffmann et al. American Journal of Psychiatry study
Can Alcohol Stop Your Period? Effects by Drinking Level
One episode of drinking does not stop the menstrual cycle. Chronic heavy drinking disrupts the HPG axis severely enough to produce anovulation, amenorrhea and menstrual cessation in women with long-term alcohol use disorder.
Both the volume and the pattern of drinking govern the answer, and the three levels below set out where each threshold sits.
Moderate Drinking and the Menstrual Cycle
Moderate alcohol consumption produces no statistically significant disruption to menstrual cycle function based on current prospective cohort research, though it consistently produces measurable hormonal changes on a per-drink basis.
There are 3 findings on moderate drinking and the cycle:
- Cycle regularity: A prospective cohort study found no statistically significant association between cycle-average moderate alcohol intake and disruption of menstrual cycle function or regularity
- Continued hormonal changes: The same study found measurable per-drink increases in estradiol and LH, indicating that even moderate drinking produces hormonal changes even when it does not noticeably disrupt cycle regularity
- Contraception interaction: Moderate alcohol consumption does not reduce the efficacy of combined oral contraceptives, though alcohol is metabolized somewhat more slowly in women using estrogen-containing contraceptives due to competitive hepatic processing
Heavy Drinking, Binge Drinking, and Menstrual Disruption
Heavy drinking, defined by the NIAAA as more than 4 drinks per day or 8 or more per week for women, produces more pronounced HPG axis suppression and is associated with clinically meaningful menstrual disruption.
- Irregular periods: Heavy drinking disrupts the LH surge frequency and amplitude enough to produce irregular cycle lengths, unpredictable ovulation timing, and heavier or lighter than normal menstrual bleeding
- Anovulatory cycles: Chronic heavy drinking suppresses the LH surge entirely, producing cycles during which no ovulation occurs; anovulatory cycles produce bleeding similar to a normal period due to estrogen withdrawal, masking the absence of ovulation
- Does alcohol make periods heavier? Yes, in heavy drinkers, elevated estrogen from both increased production and impaired hepatic clearance thickens the uterine lining beyond normal, producing heavier menstrual flow when the lining sheds
Chronic Alcohol Use Disorder and Amenorrhea
Women with long-term alcohol use disorder experience the most severe reproductive disruption, with amenorrhea (cessation of menstruation for 3 or more consecutive months) reported in a significant proportion of women in treatment for AUD.
- Hypothalamic suppression: Prolonged chronic alcohol exposure suppresses GnRH pulsatility at the hypothalamic level severely enough to halt the entire HPG cascade, resulting in amenorrhea similar to that seen in other hypothalamic-driven conditions such as functional hypothalamic amenorrhea from extreme exercise or caloric restriction
- Thyroid and adrenal contributions: Chronic heavy drinking dysregulates the HPA axis (hypothalamic-pituitary-adrenal), elevating cortisol, which independently suppresses GnRH and LH; this compound suppression from both HPG and HPA axis disruption explains the severity of menstrual cessation in AUD
- Recovery after abstinence: Menstrual cycle regularity improves with sustained abstinence as GnRH pulsatility recovers; cycle restoration begins within 3 to 6 months of sobriety, though the timeline varies with the duration and severity of prior alcohol use disorder
How Does Alcohol Reduce Fertility?
Alcohol reduces fertility through anovulation, luteal phase deficiency and elevated estrogen, each of which lowers the probability of conception and of a healthy early pregnancy.
How Does Alcohol Disrupt Ovulation?
Anovulatory cycles, disrupted LH surge timing, and shortened luteal phases from alcohol use reduce fertility through mechanisms that are distinct from but overlapping with the general NIAAA recommendation to avoid alcohol when trying to conceive.
There are 3 fertility effects of alcohol:
- Anovulation: No ovulation means no egg available for fertilization regardless of sexual timing; alcohol-driven anovulatory cycles produce normal-appearing menstrual bleeding that masks the absence of ovulation
- Luteal phase deficiency: Short luteal phases from reduced progesterone production do not provide sufficient time for embryo implantation and early pregnancy support, contributing to early pregnancy loss even when fertilization occurs
- Elevated estrogen and implantation: Abnormally elevated estrogen from alcohol use disrupts endometrial receptivity, reducing the likelihood of successful embryo implantation during an otherwise ovulatory cycle
Where Can You Get Alcohol Use Disorder Treatment in Tampa?
Riverside Recovery of Tampa treats alcohol use disorder in Tampa, Florida, addressing the hormonal and reproductive disruption alongside the disorder itself within one integrated care model.
Women with alcohol use disorder carry the general health consequences of AUD and the reproductive and hormonal disruptions documented across the clinical literature. Treatment at Riverside Recovery of Tampa covers co-occurring hormonal disruption, mood cycle effects and the AUD together.

Medical Detox and Hormonal Stabilization
Medical detox under CIWA-Ar-guided protocols removes the acute hormonal disruption caused by active heavy drinking, allowing the HPG axis to begin the process of GnRH pulsatility restoration that enables menstrual cycle normalization during sustained sobriety.
Medical detox covers 3 elements:
- Nutritional rehabilitation: Thiamine, magnesium, and B-vitamin repletion address the deficiencies from chronic heavy drinking that impair liver function and compound hormonal clearance disruption
- No BAC cutoff for admission: Women presenting in active intoxication are admitted immediately, eliminating delays that extend the period of alcohol-driven hormonal disruption
- Dual diagnosis evaluation: PMS-related mood disorders, premenstrual dysphoric disorder (PMDD), and anxiety disorders that intersect with the menstrual cycle are assessed within 72 hours of residential admission
Assistant Medical Director Erin Ikenberry, PA-C, notes: “We see women whose cycles have been disrupted for months or years before they enter treatment, and they often attribute it to stress or age without realizing how directly their drinking has been suppressing normal ovarian function. Part of our intake assessment is helping patients understand the physiological basis of what they’ve been experiencing.”
Residential and Outpatient Care
Residential treatment provides the sustained abstinence window during which HPG axis recovery begins. Alongside it, dual diagnosis programming addressing the co-occurring mood and anxiety conditions that drive the cycle-phase drinking patterns documented in the 2024 AUD research literature.
Step-down care through Day/Night Treatment and IOP supports women through the luteal-phase craving periods that research identifies as a high-risk window for relapse in women with AUD. All programs offer same-day assessments at (800) 871-5440.
Frequently Asked Questions
Can alcohol affect your period?
Yes. Alcohol disrupts the HPG axis by suppressing GnRH secretion, impairing LH and FSH release, elevating estrogen through both increased production and reduced hepatic clearance, and suppressing progesterone via luteal phase disruption. The resulting shifts in estradiol and progesterone alter cycle length, ovulation timing and menstrual flow volume, and in chronic heavy drinkers they produce irregular periods or amenorrhea.
Does alcohol affect your period if you drink occasionally?
Occasional moderate drinking produces measurable per-drink increases in estradiol and LH but is not associated with statistically significant disruption of menstrual cycle regularity in short-term research. The more relevant risk comes from heavy or binge drinking patterns and from chronic alcohol use disorder, both of which produce clinically significant hormonal disruption and menstrual irregularity.
Why does my period stop when I drink alcohol?
Alcohol suppresses the GnRH pulsatility and LH surge that trigger ovulation. Without ovulation, the corpus luteum does not form and progesterone production drops, which prevents the endometrial lining from developing normally and cause a period to be delayed, lighter, or temporarily absent. Chronic heavy drinking suppresses this axis severely enough to cause amenorrhea through hypothalamic GnRH suppression.
Does Alcohol Make Your Period Heavier?
Yes, in heavy drinkers. Alcohol elevates circulating estrogen through two mechanisms: direct stimulation of estrogen production and impairment of hepatic estrogen clearance. Elevated estrogen thickens the uterine lining beyond normal, producing heavier menstrual bleeding when the lining sheds at the end of the cycle. Binge drinking is associated with 64 percent higher free estradiol, which directly correlates with heavier menstrual flow.
Can alcohol delay your period?
Yes. Alcohol delays your period by suppressing or shifting the LH surge that triggers ovulation, pushing ovulation to a later point in the cycle and extending the follicular phase. The period then follows ovulation on the same 14-day luteal phase schedule, meaning a later ovulation produces a later period. Suppressed LH is the most common mechanism behind alcohol-associated period delays.
Does alcohol lower progesterone?
Yes. Alcohol suppresses progesterone production by disrupting the corpus luteum function that follows ovulation. A blunted or absent LH surge means a less robust corpus luteum, which produces less progesterone during the luteal phase. Progesterone deficiency shortens the luteal phase, worsens PMS symptoms, and in women with AUD, creates a cyclical hormonal environment that research links to increased luteal-phase alcohol cravings.
Can drinking alcohol induce a period?
Alcohol does not reliably induce a period. What alcohol disrupts is the hormonal balance between estrogen and progesterone enough to trigger early endometrial shedding (spotting or an early period) or cause anovulatory bleeding that resembles a period. Any alcohol-associated bleeding that is significantly earlier, later, heavier, or more irregular than usual warrants evaluation by a healthcare provider.
Can alcohol cause spotting between periods?
Yes. Alcohol-driven luteal phase disruption reduces progesterone, and low progesterone relative to estrogen produces breakthrough spotting between periods. Elevated estrogen from alcohol also increases endometrial proliferation, which produces irregular shedding and spotting independent of the normal menstrual cycle. Persistent spotting warrants gynecological evaluation regardless of alcohol use.
References
- Schliep, K. C., et al. (2015). Alcohol intake, reproductive hormones, and menstrual cycle function: A prospective cohort study. The American Journal of Clinical Nutrition, 102(4), 933–942.
- Hoffmann, S., et al. (2024). Associations of menstrual cycle and progesterone-to-estradiol ratio with alcohol consumption in alcohol use disorder. American Journal of Psychiatry, 181(5), 445–456.
- Griffith, A. K., Martel, M. M., Eisenlohr-Moul, T., & Fillmore, M. T. (2022). Heightened sensitivity to the disinhibiting effect of alcohol in women during the late follicular phase of the menstrual cycle. Experimental and Clinical Psychopharmacology, 31(4), 839–848.
- Sarkola, T., & Eriksson, C. J. P. (1999). Acute effect of alcohol on estradiol, estrone, progesterone, prolactin, cortisol, and luteinizing hormone in premenopausal women. Alcoholism: Clinical and Experimental Research, 23(6), 976–982.
- Substance Abuse and Mental Health Services Administration. (2023). National Survey on Drug Use and Health, 2022 results. U.S. Department of Health and Human Services.
- National Institute on Alcohol Abuse and Alcoholism. (2023). Women and alcohol. Retrieved from niaaa.nih.gov
- American Psychiatric Association. (2022). Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR). American Psychiatric Publishing.